Health & Medicine
How to Help Someone With Depression
Which advice for supporters has been tested, and which is charity guidance.
Health & Medicine
What Is Anorexia Nervosa?
What it is, how dangerous it is, whether it is a choice, and what treatment and help have been shown to do.
Health & Medicine
Does Social Media Harm Teenagers’ Mental Health?
What the surveys, cohort studies and meta-analyses show, and how big the effects are.
What Is Depression?
Two people can both be diagnosed with major depression and share no symptom. This page sets out what the diagnosis requires, how common and how dangerous depression is, and what is known about its causes. It also covers what treatment does, and why more treatment has not meant less depression.
Jump to the verdict ↓
What this covers
This page contains no description of methods of self-harm and no drug doses, anywhere, including where a cited study involved them. Crisis numbers, and a link to this site's page on supporting someone with depression, are under Help now, just before the verdict.
What the diagnosis requires
A major depressive episode requires five of nine symptoms in the same two-week period. At least one of them has to be low mood or loss of interest or pleasure, lasting most of the day, nearly every day. Four of the other seven are significant weight change or a change in appetite, insomnia or sleeping too much, agitation or slowing that someone else can see, and fatigue. The rest are worthlessness or misplaced guilt, trouble concentrating or deciding, and recurrent thoughts of death or suicide, or a suicide attempt.
The symptoms have to be new or clearly worse than before, and they have to cause clinically significant distress or impairment. Two editions of the American Psychiatric Association's Diagnostic and Statistical Manual of Mental Disorders (DSM), DSM-IV in 1994 and DSM-5 in 2013, list the same nine symptoms. DSM-5-TR in 2022 kept them, rewording the suicide symptom and an exclusion for psychotic disorders.
One 2013 change was to delete the bereavement exclusion, and the Substance Abuse and Mental Health Services Administration counts it among DSM-5's more controversial changes. The exclusion had advised clinicians not to diagnose major depression in the first two months after the death of a loved one, unless certain serious symptoms were present. Suicidal thoughts and psychotic symptoms were among them.
The American Psychiatric Association pointed out that no other stressor, such as losing a job, blocked the diagnosis. The administration's report gives further reasons for the change: depression after a death has similar risk factors and course to other depression, and responds to the same treatments.
Jerome Wakefield and Michael First argued that there was no scientific basis for the removal, and that some normal grief could be misdiagnosed as major depression. DSM-5-TR later added prolonged grief disorder. In adults, it covers grief that still causes clinically significant distress or impairment more than 12 months after the death. DSM-5-TR says both diagnoses are given when both are met.
Alongside the episodic form there is persistent depressive disorder: low mood most of the day, more days than not, for at least two years in adults. It also needs two of six further symptoms, with no gap longer than two months. It merged what used to be dysthymia and chronic major depression.
Two people, no shared symptoms
Five of nine, one of which must be from a fixed pair, allows 227 different ways to qualify. Three of the criteria are two-sided. You can meet the sleep item by sleeping far too little or far too much, and the appetite item by eating far too little or far too much. The psychomotor item can be met by agitation or by slowing. Count those poles separately and the number goes to 945. Count the sub-parts of most compound items too, as Coomans and Fried did, and it reaches 10,377.
So one person can have low mood, insomnia, poor appetite, agitation and guilt. Another can have lost interest and pleasure, and be sleeping far too much, eating far more, slowed down and unable to concentrate. Both meet the criteria for major depression, and they share no symptom.
Symptom combinations found in two samples of patients with major depression
Zimmerman: patients interviewed with semi-structured interviews; Fried and Nesse: outpatients in the STAR*D trial, 12 symptoms
Zimmerman 2015 — patientsmore than 1,500
Combinations of the nine criteria found, of 227 possible170
Commonest pattern (all nine criteria)10.1%
Fried & Nesse 2015 — patients3,703
Distinct symptom profiles found1,030
Profiles held by exactly one person501 (48.6%)
Commonest profile (no symptom above the study's cut-off)1.8%
Zimmerman and colleagues add that nine combinations, a relatively small number, accounted for more than 40% of the patients diagnosed.
Fried and Nesse used the baseline data from STAR*D (Sequenced Treatment Alternatives to Relieve Depression), one of the largest clinical trials of depression. In that trial, the 501 profiles held by a single person mean that roughly one patient in seven had a symptom picture shared with nobody else. Controlling for how severe people were did not reduce the spread.
Fried has also shown that seven common depression rating scales between them contain 52 distinct symptoms. The scales overlap by about a third on average (0.36, on a measure from 0 for no overlap to 1 for full overlap). He concludes that research results may depend on which scale a study used.
The melancholic subtype does not narrow the number of ways to qualify. On Coomans and Fried's counts, depression with melancholic features can be met in 10,999 to 341,737 ways, more than major depression itself.
Fried and Nesse conclude that depression is not one coherent condition with a single cause. They weigh this against the view that it is one disease with varied symptoms. That view, they say, remains possible but is increasingly unlikely, because no biomarker for it has been replicated.
How common it is
Three American national surveys of adults put lifetime prevalence of major depression at about 13% to about 21%.
US prevalence of major depression by survey
National Comorbidity Survey Replication (NCS-R) and National Epidemiologic Survey on Alcohol and Related Conditions (NESARC): face-to-face national surveys, different instruments
NCS-R (2001–02, n=9,090) — 12-month6.6%
NCS-R — lifetime16.2%
NESARC-I (2001–02) — lifetime13.2%
NESARC-III (2012–13, n=36,309) — 12-month10.4%
NESARC-III — lifetime20.6%
The surveys used different interviews, and NESARC-III applied DSM-5, the diagnostic manual's 2013 edition, which no longer excludes bereavement. NESARC-III's authors wrote that dropping the exclusion could explain a small amount of the increase since NESARC-I, not all of it, and that other national reports support a real one. NESARC-I and NESARC-III both found women at higher risk; in NESARC-III, men's odds of past-year depression were half women's.
Whether depression is becoming more common is not settled. Compton and colleagues found past-year prevalence among US adults rising from 3.33% in 1991–92 to 7.06% in 2001–02, on the same criteria. The Stirling County Study in Atlantic Canada found current depression stable at about 5% in samples from 1952, 1970 and 1992, on its own measures. Ormel and colleagues, reviewing the evidence in 2022, found little evidence that prevalence has risen.
How dangerous it is
People with depression die at roughly twice the rate of people without it. A 2025 review in World Psychiatry pooled 268 cohort studies and 10.8 million people with depression. It put all-cause mortality at a relative risk of 2.10 (95% confidence interval 1.87 to 2.35). Against people matched for their other medical conditions, the relative risk was still 1.29.
Suicide carries the highest relative risk in that review, 9.89, but the authors note, citing earlier studies, that the excess deaths are mainly from natural causes. A Danish register study shows both.
| Cause of death | Diagnosed with depression | Matched reference population |
|---|---|---|
| Any cause | 21.9% | 11.2% |
| Suicide | 2.5% | 0.2% |
| Cardiovascular disease | 4.3% | 3.0% |
| Respiratory disease, including lung cancer | 3.2% | 2.0% |
| Cancer, excluding lung cancer | 3.1% | 2.7% |
Osler and colleagues, 2025: 330,577 adults diagnosed with major depression in Danish hospital registers from 1970 to 2021, and five matched people for each. Cumulative risk of death ten years after diagnosis.
In the first year after diagnosis, suicide was the leading cause of death among the Danish patients, at 0.9%, and it was also the leading cause before age 65.
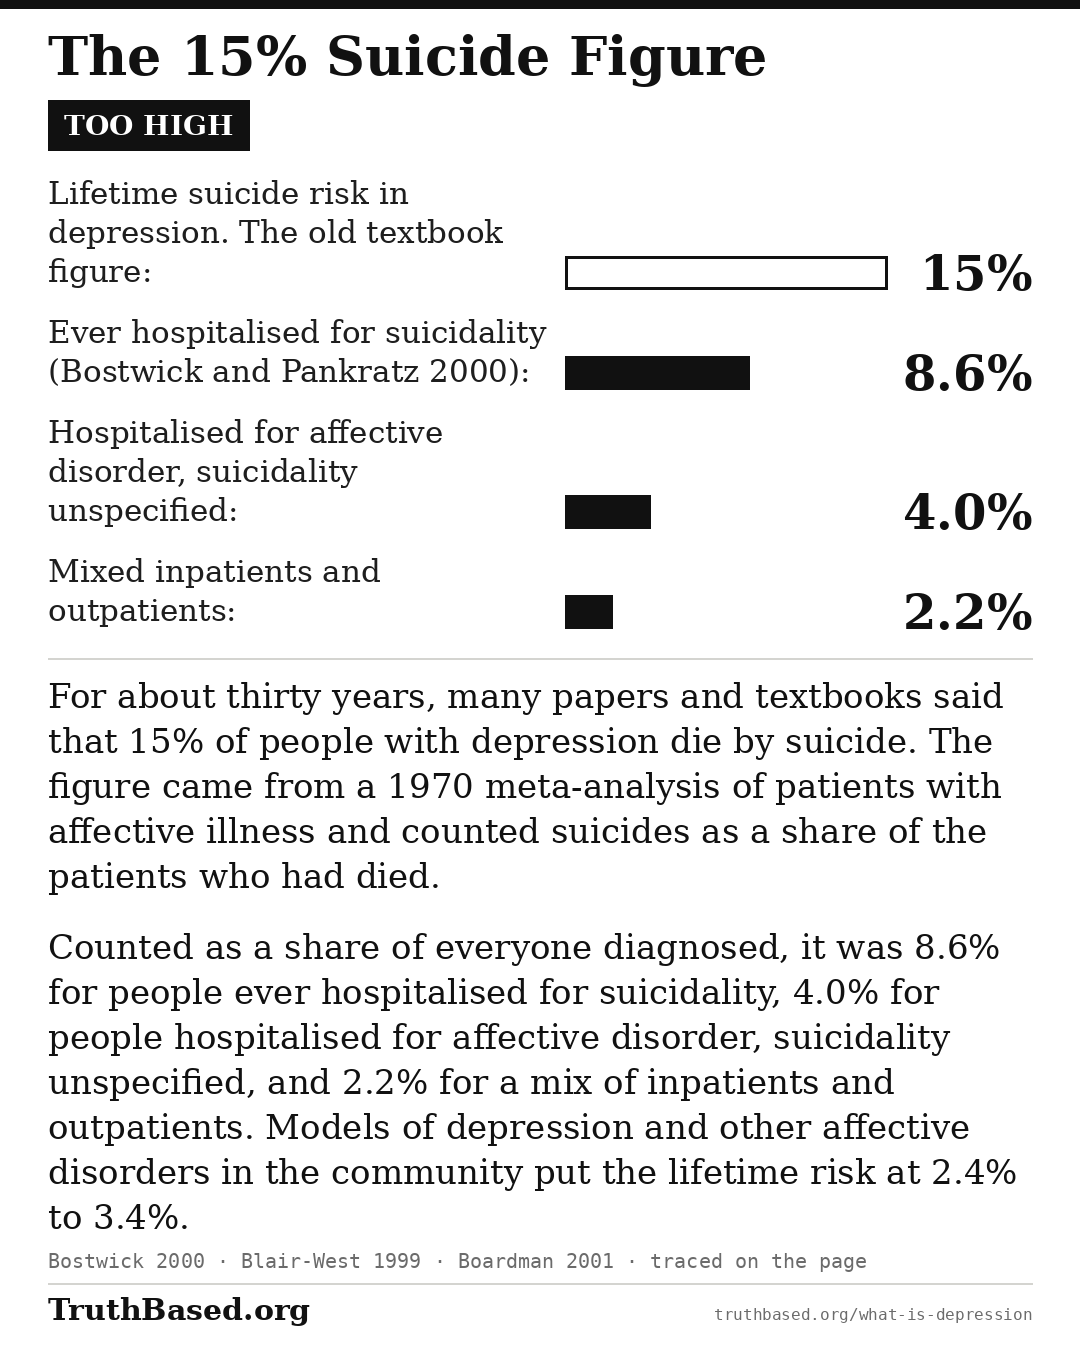
The 15% figure, and why it was wrongFor about thirty years, many papers and textbooks repeated that 15% of people with depression die by suicide. As Bostwick and Pankratz put it in 2000, the figure came from Guze and Robins's 1970 meta-analysis of patients with affective illness and was then applied to all depression.
Bostwick and Pankratz argued that the figure used a less appropriate measure: suicides as a share of the patients who had died, called proportionate mortality. They recalculated it as case fatality, suicides as a share of everyone diagnosed, and split it by treatment setting.
Lifetime suicide risk by treatment setting
Bostwick & Pankratz 2000, case-fatality method
Ever hospitalised for suicidality8.6%
Hospitalised for affective disorder, suicidality not specified4.0%
Mixed inpatient and outpatient2.2%
People without affective illnessunder 0.5%
Blair-West and colleagues worked from population figures: given how common major depression is and how many suicides occur, the lifetime risk cannot be 15%. Their 1999 estimate was 3.4%. By sex, it was about 7% for men and 1% for women. Boardman and Healy modelled 212 suicides in one English health district against community prevalence rates. They got 2.4% for any affective disorder, and 1.1% for cases without substance misuse, personality disorder or non-affective psychosis that had never reached mental health services.
The risk is highest in the first year after diagnosis and among people who have been in hospital. In the Danish register study, the lifetime risk of suicide was 11.2% for people diagnosed with depression by hospital services, against 1% in the matched population.
Download this conclusion: the 15% figure
Disability and course
This section as one image: the old 15% figure, the lifetime risks of 8.6%, 4.0% and 2.2% by treatment setting, and the 2.4% to 3.4% that population models give.
Depression ranked second among all causes of years lived with disability worldwide in the 2019 Global Burden of Disease estimates, and thirteenth for total burden. Its total burden counts no deaths, because the estimates file suicide under injuries. Depression's figures are modelled: estimated prevalence multiplied by disability weights. The weights come from surveys asking people which of two described health states is healthier, and from questions placing them on a scale from perfect health to death.
Course has been followed both in the general population and in clinic patients, though the studies define recovery and recurrence differently. Eaton and colleagues followed 92 people in Baltimore through their first lifetime episode, in a study with 23 years of follow-up. Around half recovered and never had another episode. Of the 78 who recovered, 35 later recurred. Roughly 15% of the 92 had no year free of it. Median episode length was twelve weeks, though the first episode lasted a median of 20 weeks.
The National Institute of Mental Health's Collaborative Program on the Psychobiology of Depression followed 318 patients in its clinical studies for ten years. Nearly two-thirds had at least one recurrence.
Is it a choice?
A 2000 review of family, adoption and twin studies concluded that major depression results from both genetic and environmental influences, not from either alone. The research on causes asks how much of depression comes from genes, how much from circumstance, and whether effort changes it.
Twin studies put heritability at 37%, from that review's meta-analysis by Sullivan, Neale and Kendler, who called this probably the lower bound. They put the likely range at 31% to 42%. A Swedish national twin study put it at 42% for women and 29% for men. Shared family environment contributes almost nothing; the rest is environment specific to the individual, together with measurement error. Measured directly from genetic data, common variants account for about 9%, around a quarter of the twin estimate.
Large genome-wide studies found 44 associated variants in 2018, then 102 in 2019. A genetic risk score from the 2018 study ranked a person with depression above one without 57% of the time. A coin does it 50% of the time.
The candidate-gene collapseBefore genome-wide methods, the field tested single plausible genes in samples far smaller than today's. One of the best-known results was Caspi and colleagues' in 2003. Carriers of one or two short versions of a stretch of the serotonin transporter gene, 5-HTTLPR, had more depression after stressful life events than people with two long versions.
Culverhouse and colleagues tested Caspi's result in 38,802 people of European ancestry. They found no subgroup or definition in which the interaction was statistically significant, while stress itself was a strong risk factor. Border and colleagues tested eighteen candidate genes, in samples of 62,138 to 443,264 people. They found no clear evidence for any of them, alone or with the environment. Their results, they concluded, suggest that the many associations reported in that literature are likely to be false positives.
SerotoninMoncrieff and colleagues published an umbrella review in 2022 covering six areas of serotonin research. They concluded there is no consistent evidence of an association between serotonin and depression, and no support for the idea that depression is caused by lowered serotonin.
Jauhar, Cowen and more than thirty co-authors replied in 2023 that Moncrieff's conclusion was overstated, and that the review was not a standard umbrella review. They also said its certainty ratings used a modified version of a standard system, added after the review's protocol was set. Moncrieff and colleagues answered that they had synthesised all existing studies in the main areas, and that the onus is on others to make a convincing case. Whether antidepressants work is a separate question, tested by the trials in the next section.
Circumstance, and whether effort moves itStressful life events predict the onset of depression. In a 1999 study of female twins by Kendler and colleagues, the comparison within identical twin pairs held their shared genes constant. Even within those pairs, the odds of a new episode were 3.58 times higher in the month of a stressful event. The authors still judged about a third of the overall link non-causal.
Brown and Harris found depression more common among working-class women in Camberwell, in London. By the University of Essex's account, they tied the difference to life events and to vulnerability factors, such as having no one to confide in.
A procedural replication in Calgary, published in 1982, found no link between new episodes in the past year and social class, employment or the number of children at home. But it confirmed the links with severe life events and difficulties, and with lacking intimacy with a partner. It concluded that the role of social factors is community-specific, and that the causal role of events and difficulties remains uncertain.
Behavioural activation is a therapy that uses scheduled activities to help people reconnect with what they find rewarding. A 2026 review gathered 105 trials of it, with 13,933 patients. In 61 comparisons with control conditions in adult outpatients, its standardised mean difference was 0.67. The effect was still significant 12 months after randomisation.
Against other therapies, in 27 comparisons, the difference was not significant. Across the 61 control comparisons, heterogeneity was high and the prediction interval crosses zero, so a new trial could find no benefit. Self-guided behavioural activation also worked, with a smaller effect of 0.36.
What treatment does
In 2018, Cipriani and colleagues pooled 522 double-blind trials covering 116,477 adults. The trials covered 21 antidepressants, and all 21 beat placebo. The odds ratios for response, meaning symptom scores fell by at least half, ran from 2.13 for amitriptyline down to 1.37 for reboxetine. The overall drug-placebo difference came to a standardised mean difference of 0.30. Nine per cent of the trials were rated high risk of bias, 73% moderate, and the authors graded the certainty of the evidence as moderate to very low.
Irving Kirsch and colleagues worked from the Food and Drug Administration's own data on four newer antidepressants. They put the pooled difference at 1.8 points on the Hamilton scale. Drug groups improved by 9.6 points and placebo groups by 7.8. The National Institute for Health and Care Excellence (NICE) had defined a clinically significant benefit as a 3-point difference or a standardised mean difference of 0.50. The pooled difference, a standardised mean difference of 0.32, falls short of both.
Fountoulakis and Möller recalculated Kirsch's data and got 2.18 or 2.68 points. Venlafaxine and paroxetine came out above 3. Kirsch and colleagues replied that the recalculation weighted the trials wrongly; done correctly, no single drug reached NICE's criterion. The recalculation's own standardised effect size matched theirs, substantially below the criterion.
Turner and colleagues showed why the published literature looks better than the drugs are. Of 74 trials registered with the Food and Drug Administration (FDA), 31% were not published. By the FDA's reading 51% were positive; in the published record 94% appeared positive. The effect size in print was 0.41, against 0.31 in the FDA's data for all trials, published and unpublished alike.
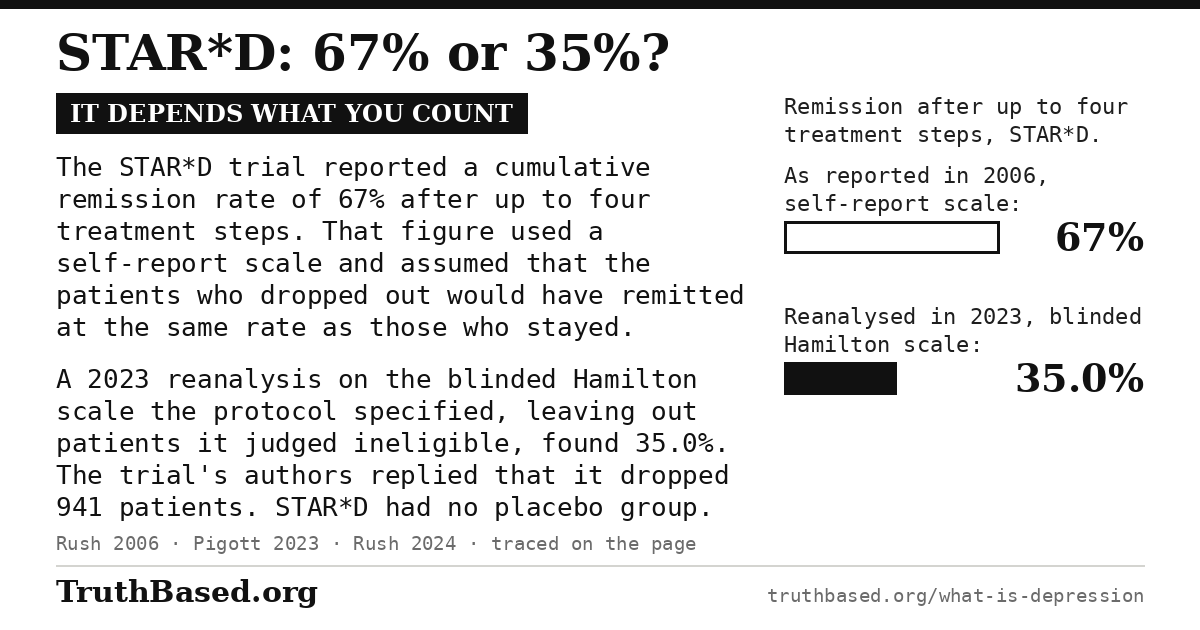
STAR*DThe headline figure of the STAR*D (Sequenced Treatment Alternatives to Relieve Depression) trial came from Rush and colleagues in 2006. It is a cumulative remission rate of 67% after up to four sequential treatment steps. The trial's report called that figure theoretical: it assumed that the people who dropped out would have remitted at the same rate as those who stayed. In Pigott and colleagues' reanalysis, 53.7% dropped out.
Pigott and colleagues reanalysed the patient-level data in 2023, following the trial's protocol and, where it was silent, the trial's other papers. The protocol specified the Hamilton scale, given by blinded research assessors, rather than the self-report scale behind the 67%. Following the other papers, they excluded patients the published analysis had included. They got 35.0%, or 41.3% when patients with no final Hamilton score are also counted if their last self-report score showed remission.
Rush and colleagues replied that the reanalysis dropped 941 patients. The difference in remission rates, they said, was most likely the result of excluding hundreds with low symptom scores when they left. They also pointed to a separate study, co-authored by Pigott's senior author, that found 60% remission over 12 months of antidepressant treatment.
A third analysis, by Sakurai and colleagues in 2024, used the self-report scale and weighted for dropout. It estimated 53.8% at 90 days and 74.5% at six months. At a year, the estimate was 87.5%. One dataset, three numbers, none of them from a placebo-controlled trial, because STAR*D had no placebo arm.
Download this conclusion: STAR*D
Psychotherapy, and what happens when you allow for quality
This section as one image: the 67% STAR*D reported, the 35.0% a reanalysis found on the measure the trial's protocol specified, and what each assumed.
Cuijpers and colleagues have measured how far the literature on psychotherapy for depression overstates its effects. Their 2010 meta-analysis found an overall effect size of 0.67, falling to 0.42 once publication bias was accounted for. In 2019 they adjusted for risk of bias, publication bias and waiting-list controls together, and left out trials from non-Western countries. The pooled figure fell from an unadjusted 0.70 to 0.31. Only 23% of the studies were at low risk of bias.
Munder and eight co-authors reanalysed the same effect sizes, treating waiting lists as the right comparison and removing outliers. They found about 0.70 against waiting lists and 0.31 against usual care. Cuijpers and colleagues replied in the same journal.
A 2021 network meta-analysis of 331 trials by Cuijpers and colleagues compared psychotherapies. Cognitive behavioural therapy, behavioural activation, interpersonal therapy and psychodynamic therapy did not differ significantly from each other; only non-directive supportive counselling did worse.
ExerciseA 2024 network meta-analysis in the BMJ compared exercise with active controls such as usual care. It covered 218 studies. Their 495 arms held 14,170 participants.
| Kind of exercise | g |
|---|---|
| Walking or jogging | -0.63 |
| Yoga | -0.55 |
| Strength training | -0.49 |
| Dance (107 participants) | -0.96 |
Only one of the 218 studies met Cochrane's criteria for low risk of bias. The authors rated their confidence low for walking or jogging and very low for every other kind of exercise. They conclude that exercise is an effective treatment; how large its effect is remains uncertain.
Coming off antidepressantsDavies and Read's 2019 review of the withdrawal literature reported a weighted average incidence of 56%. Across its studies, incidence ranged from 27% to 86%. In four large studies, 46% of those affected chose the most severe rating offered. Jauhar, Hayes and colleagues replied that these estimates leaned on convenience-sample surveys, two of them of people who reported withdrawal needing treatment. Such surveys, they wrote, cannot be extended to everyone taking antidepressants.
Henssler and colleagues pooled 79 studies in 2024. They found at least one symptom in 31% of patients stopping an antidepressant, against 17% of those stopping a placebo. Severe symptoms were rarer: 2.8% against 0.6%.
The numbers are still disputed, but the guidance moved. In 2019 the Royal College of Psychiatrists said some patients can suffer more severe symptoms that can last much longer. It asked NICE to update its advice, which suggested most people should be able to come off antidepressants over four weeks. NICE now says the dose should be reduced in stages.
More treatment, no less depression
In the United States, outpatient treatment for depression rose from 0.73 people in every 100 in 1987 to 2.33 in 1997. By 2007 it was 2.88, about four times the 1987 rate.
Ormel, Hollon, Kessler, Cuijpers and Monroe reviewed this in 2022 and called it the treatment-prevalence paradox. In their account, treatments have improved and become far more available since the 1980s, but the prevalence of depression has not decreased.
They found little evidence that more misdiagnosis or more new cases had hidden a real fall. They concluded that three explanations probably account for most of the paradox:
- published trials overstate how well treatments work;
- treatments work considerably less well in ordinary clinics than in trials;
- treatment's impact differs substantially between non-recurrent cases and chronic or recurrent ones, which make up most of the depression in a population at any one time.
This does not mean the treatments do nothing: in trials, antidepressants beat placebo and psychotherapy beats control conditions, by modest amounts.
In 2023 Mulder and Jorm compared countries in the Organisation for Economic Co-operation and Development (OECD). Countries prescribing more antidepressants, they found, did not have less sadness, worry or unhappiness. For worry, the link came close to statistical significance in the opposite direction: more prescribing, more worry. Countries with a higher Human Development Index, which combines income, education and life expectancy, had less of all three.
Help now
If you need help now
United States. The 988 Suicide and Crisis Lifeline takes calls and texts at any hour, free and confidential, in English and Spanish, with phone interpreters for more than 240 other languages. Veterans, active service members and their loved ones press 1. You do not have to be suicidal to call 988. The Crisis Text Line answers texts around the clock: text HOME to 741741. In an emergency, 911.
United Kingdom and Ireland. Samaritans answer on 116 123, free from any phone, at any hour of any day, and the number does not appear on your bill. In Ireland, Samaritans say that from 9 November 2026 they will not connect calls from withheld numbers. In an emergency in Ireland, call 112 or 999.
United Kingdom. A Welsh-language Samaritans line runs on 0808 164 0123, every day from 7pm to 11pm. If you would rather write than speak, Shout takes texts at any hour: text SHOUT to 85258. CALM's suicide prevention helpline, for anyone over 18 affected by suicide or suicidal thoughts, is on 0800 58 58 58 from 5pm to midnight every day. For urgent NHS mental health help in England, Scotland or Wales, call 111 and choose the mental health option (in Wales, press 2), and 999 in an emergency.
PAPYRUS entered administration on 7 September 2026, and its HOPELINE247 helpline, 0800 068 4141, no longer operates, though some council directories still list it. Use Samaritans or Shout instead. Samaritans retired their text service on 4 February 2020, so a Samaritans text number no longer works; they point texters to Shout.
The rest of it
Supporting someone who is depressed has its own research literature and its own page: How to Help Someone With Depression. It covers what to say and what not to, why asking someone directly about suicide has not been found to raise their risk, and what the law allows when someone refuses help.
The verdict: what the evidence shows
Major depression is diagnosed from a checklist of five of nine symptoms over two weeks. The criteria can be met in 227 ways. Because some symptoms can run in opposite directions, such as sleeping too little or too much, two people with the same diagnosis can share no symptom.
People with depression die at about twice the rate of others, mainly of natural causes, though suicide carries the highest relative risk. For depression and other affective disorders in the community, models put the lifetime risk of suicide at 2.4% to 3.4%. That is far below the old figure of 15%.
Genes and circumstance both play a part. Twin studies put heritability at 37%, probably a lower bound, and stressful events raise the odds of an episode even within identical twin pairs. Moncrieff and colleagues' 2022 review found no support for the idea that low serotonin causes depression; its critics call that conclusion overstated.
Treatment helps, modestly. Antidepressants beat placebo by a standardised mean difference of 0.30. Psychotherapy's effect falls from 0.70 to 0.31 once trial quality, waiting-list comparisons and publication bias are allowed for and non-Western trials are left out. Exercise helps, by an amount that weak trials leave uncertain.
Yet as treatment has spread, the prevalence of depression has not fallen. Ormel and colleagues' 2022 review concluded that overstated trial results, weaker results in ordinary clinics and a different impact on chronic and recurrent cases probably account for most of that.
Five common claims, against the evidence
Claim“Depression is caused by low serotonin.”
No consistent evidenceMoncrieff and colleagues' 2022 review of six areas of serotonin research found no support for the idea that depression is caused by lowered serotonin. More than thirty researchers replied that its conclusion was overstated. Whether antidepressants work is a separate question, tested by trials.
Claim“Antidepressants work no better than a placebo.”
Better, modestlyAll 21 antidepressants in a 2018 review beat placebo; pooled, the standardised mean difference was 0.30. On the Food and Drug Administration's data for four newer drugs, the difference was 1.8 points on the Hamilton scale. That is short of the 3 points the National Institute for Health and Care Excellence had set as clinically significant. A reanalysis put it at 2.18 or 2.68 points; the original authors replied that it weighted the trials wrongly.
Claim“Two-thirds of patients get well if they keep trying antidepressants.”
DisputedThat is the 67% reported by the STAR*D (Sequenced Treatment Alternatives to Relieve Depression) trial. It assumed that the patients who dropped out would have done as well as those who stayed. A reanalysis on the blinded Hamilton scale the trial's protocol specified found 35.0%. The trial had no placebo group.
Claim“15% of people with depression die by suicide.”
Too highThe figure came from patients with affective illness and counted suicides as a share of the patients who had died. Population models put the lifetime risk at 2.4% to 3.4% for depression and other affective disorders in the community. In Denmark it was 11.2% for people diagnosed by hospital services.
Claim“More treatment will mean less depression.”
Not so farOutpatient treatment in the United States rose about fourfold from 1987 to 2007, and the prevalence of depression has not fallen. Across the countries of the Organisation for Economic Co-operation and Development, more antidepressant prescribing went with no less sadness, worry or unhappiness.
Download the conclusion
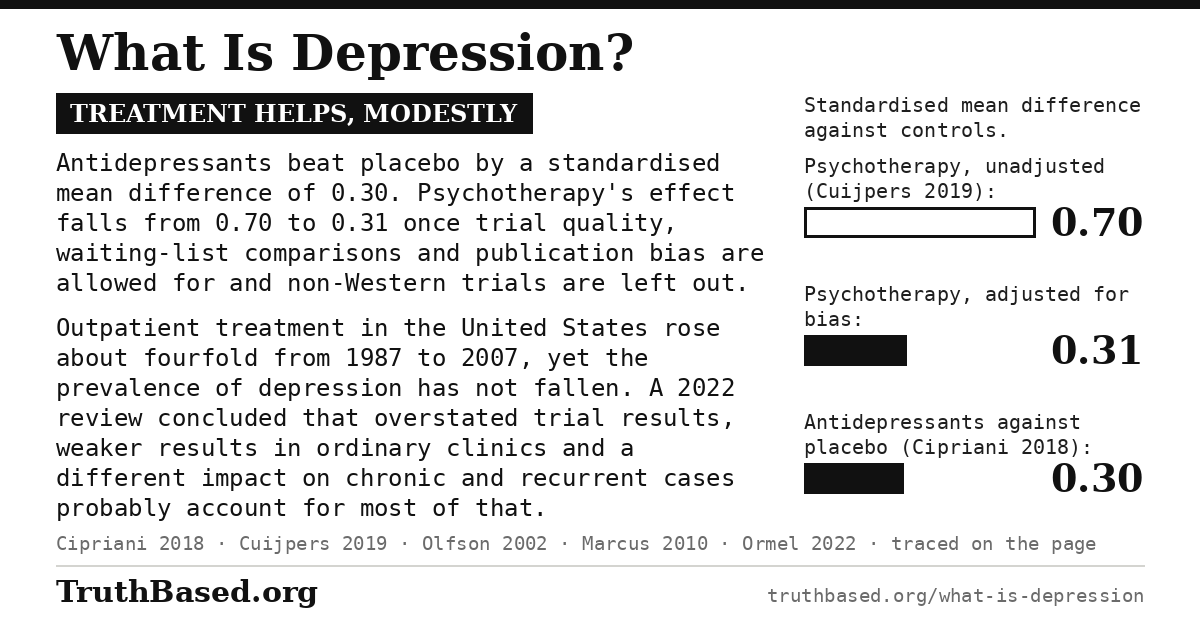
The verdict on treatment as one image, with the three numbers that frame it. Antidepressants beat placebo by a standardised mean difference of 0.30. Psychotherapy's effect is 0.70 before allowing for bias and 0.31 after. The image is 1,200 by 630 pixels, the size social networks use for link previews, and anyone may download it and post it.
What would change this conclusion
This article concludes that: (1) major depression is a broad diagnosis, met by many different combinations of symptoms; (2) people with depression die at about twice the usual rate, mostly of natural causes, and for depression in the community the lifetime risk of suicide is far below 15%; (3) genes and circumstance both contribute, and the evidence does not show that low serotonin causes depression; (4) antidepressants and psychotherapy help, by modest amounts; (5) more treatment has not lowered the prevalence of depression.
These conclusions would be falsified by:
• Placebo-controlled trials at low risk of bias finding effects for antidepressants or psychotherapy well above a standardised mean difference of about 0.3
• Population surveys repeated on the same criteria showing the prevalence of depression falling as treatment spreads
• Consistent evidence, across the areas of serotonin research, that lowered serotonin comes before depression
• Long follow-ups of people with depression in the community finding a lifetime suicide risk near 15%
Sources
Substance Abuse and Mental Health Services Administration (SAMHSA), Center for Behavioral Health Statistics and Quality. Impact of the DSM-IV to DSM-5 Changes on the National Survey on Drug Use and Health. June 2016. Source for the criteria for a major depressive episode (five or more of nine symptoms in two weeks, one being low mood or loss of interest or pleasure), the symptoms DSM-IV and DSM-5 share, the removal of the bereavement exclusion, which SAMHSA counts among DSM-5's more controversial changes, the reasons given for it, and the criteria for persistent depressive disorder, which merged dysthymia and chronic major depression. samhsa.gov
American Psychiatric Association. DSM-5-TR fact sheet: Major Depressive Disorder. 2022. Source for the DSM-5-TR wording of the psychotic-disorder exclusion. psychiatry.org
American Psychiatric Association. DSM-5-TR Update, September 2022. Source for the changes DSM-5-TR made to the depression criteria, including the suicide symptom, and its description of prolonged grief disorder. psychiatry.org
American Psychiatric Association. Major Depressive Disorder and the “Bereavement Exclusion”. Fact sheet, 2013. Source for the APA's argument that no other stressor blocked the diagnosis. psychiatry.org
Wakefield JC, First MB. Validity of the bereavement exclusion to major depression: does the empirical evidence support the proposal to eliminate the exclusion in DSM-5? World Psychiatry, 2012;11(1):3–10. Source for the argument against removing the bereavement exclusion. pmc.ncbi.nlm.nih.gov
American Psychiatric Association. APA Offers Tips for Understanding Prolonged Grief Disorder. News release, 2021. Source for prolonged grief disorder, added in DSM-5-TR. psychiatry.org
Coomans F, Fried EI. Counting unique symptom profiles of Major Depressive Disorder and Major Depressive Disorder with melancholic features. Calculation note, undated, linked from Fried EI, 10,377 ways for major depression, but 341,737 ways for melancholia, blog post, 19 July 2018. Source for the 227 and 10,377 ways to meet the criteria, and the 10,999 to 341,737 ways for melancholic features. media.eiko-fried.com
Fried EI, Nesse RM. Depression is not a consistent syndrome: an investigation of unique symptom patterns in the STAR*D study. Journal of Affective Disorders, 2015;172:96–102. Source for the 945 ways to meet the criteria when the two-sided symptoms are counted by direction, the 1,030 symptom profiles among 3,703 patients, the 501 profiles held by one person, the commonest profile at 1.8%, the point that two people can meet the criteria with no symptom in common, and the authors' view of one disease against several. pmc.ncbi.nlm.nih.gov
Zimmerman M, Ellison W, Young D, Chelminski I, Dalrymple K. How many different ways do patients meet the diagnostic criteria for major depressive disorder? Comprehensive Psychiatry, 2015;56:29–34. Source for the more than 1,500 patients, the 170 of 227 combinations found, and the commonest pattern, all nine criteria, at 10.1%. pubmed.ncbi.nlm.nih.gov
Fried EI. The 52 symptoms of major depression: lack of content overlap among seven common depression scales. Journal of Affective Disorders, 2017;208:191–197. Source for the 52 symptoms across seven rating scales and their mean overlap of 0.36. dare.uva.nl
Lorenzo-Luaces L, Buss JF, Fried EI. Heterogeneity in major depression and its melancholic and atypical specifiers: a secondary analysis of STAR*D. BMC Psychiatry, 2021;21:454. Source for the counts of ways to meet the criteria with and without the melancholic specifier. pmc.ncbi.nlm.nih.gov
Kessler RC, Berglund P, Demler O, et al. The epidemiology of major depressive disorder: results from the National Comorbidity Survey Replication (NCS-R). JAMA, 2003;289(23):3095–3105. Source for the NCS-R's 12-month and lifetime prevalence, 6.6% and 16.2%, in 9,090 adults surveyed in 2001–02. pubmed.ncbi.nlm.nih.gov
Hasin DS, Goodwin RD, Stinson FS, Grant BF. Epidemiology of major depressive disorder: results from the National Epidemiologic Survey on Alcoholism and Related Conditions. Archives of General Psychiatry, 2005;62(10):1097–1106. Source for NESARC-I's lifetime prevalence of 13.2% and its finding that women were at higher risk. doi.org
Hasin DS, Sarvet AL, Meyers JL, et al. Epidemiology of adult DSM-5 major depressive disorder and its specifiers in the United States. JAMA Psychiatry, 2018;75(4):336–346. Source for NESARC-III's 12-month and lifetime prevalence, 10.4% and 20.6%, in 36,309 adults surveyed in 2012–13, and men's odds of past-year depression at half women's. pubmed.ncbi.nlm.nih.gov
Compton WM, Conway KP, Stinson FS, Grant BF. Changes in the prevalence of major depression and comorbid substance use disorders in the United States between 1991–1992 and 2001–2002. American Journal of Psychiatry, 2006;163(12):2141–2147. Source for past-year prevalence rising from 3.33% to 7.06%. rti.org
Murphy JM, Laird NM, Monson RR, Sobol AM, Leighton AH. A 40-year perspective on the prevalence of depression: the Stirling County Study. Archives of General Psychiatry, 2000;57(3):209–215. Source for current depression stable at about 5% in 1952, 1970 and 1992. doi.org
Ormel J, Hollon SD, Kessler RC, Cuijpers P, Monroe SM. More treatment but no less depression: the treatment-prevalence paradox. Clinical Psychology Review, 2022;91:102111. Source for treatments improving and spreading since the 1980s while prevalence has not decreased, the little evidence that misdiagnosis or new cases rose, and the three explanations that probably account for most of the paradox. pubmed.ncbi.nlm.nih.gov
Chan JKN, Solmi M, Lo HKY, et al. All-cause and cause-specific mortality in people with depression: a large-scale systematic review and meta-analysis of relative risk and aggravating or attenuating factors, including antidepressant treatment. World Psychiatry, 2025;24(3):404–421. Source for the 268 cohort studies and 10.8 million people with depression, the all-cause relative risk of 2.10 (95% CI 1.87 to 2.35), 1.29 against people matched for their other conditions, suicide's relative risk of 9.89, and the authors' statement, citing earlier studies, that the excess deaths are mainly from natural causes. pmc.ncbi.nlm.nih.gov
Osler M, Rosenqvist TW, Bjørn-Rozing MP, et al. All-cause and cause-specific mortality among individuals with major depression: a nationwide Danish matched-cohort study. Acta Psychiatrica Scandinavica, 2025;152(1):60–68. Source for the table of deaths by cause ten years after diagnosis, suicide as the leading cause of death in the first year and before age 65, and the lifetime suicide risk of 11.2% against 1%. pmc.ncbi.nlm.nih.gov
Bostwick JM, Pankratz VS. Affective disorders and suicide risk: a reexamination. American Journal of Psychiatry, 2000;157(12):1925–1932. Source for the 15% figure's origin in Guze and Robins's 1970 meta-analysis and its use for all depression, the case-fatality method, and the lifetime risks by treatment setting: 8.6%, 4.0%, 2.2% and under 0.5%. doi.org
Blair-West GW, Cantor CH, Mellsop GW, Eyeson-Annan ML. Lifetime suicide risk in major depression: sex and age determinants. Journal of Affective Disorders, 1999;55(2–3):171–178. Source for the lifetime risk of 3.4%, about 7% for men and 1% for women, and why it cannot be 15%. doi.org
Boardman AP, Healy D. Modelling suicide risk in affective disorders. European Psychiatry, 2001;16(7):400–405. Source for the 212 suicides in one English district, and the lifetime risks of 2.4% for any affective disorder and 1.1% for uncomplicated cases with no service contact. doi.org
GBD 2019 Mental Disorders Collaborators. Global, regional, and national burden of 12 mental disorders in 204 countries and territories, 1990–2019: a systematic analysis for the Global Burden of Disease Study 2019. The Lancet Psychiatry, 2022;9(2):137–150. Source for depression's ranks, second for years lived with disability and thirteenth for total burden, and how disability weights are made. pmc.ncbi.nlm.nih.gov
Eaton WW, Shao H, Nestadt G, Lee HB, Bienvenu OJ, Zandi P. Population-based study of first onset and chronicity in major depressive disorder. Archives of General Psychiatry, 2008;65(5):513–520. Source for the 92 Baltimore people followed from a first episode, the shares who recovered for good, recurred or had no year free of it, and the median episode lengths. pmc.ncbi.nlm.nih.gov
Solomon DA, Keller MB, Leon AC, et al. Multiple recurrences of major depressive disorder. American Journal of Psychiatry, 2000;157(2):229–233. Source for the 318 patients followed for ten years, nearly two-thirds of whom had at least one recurrence. doi.org
Mueller TI, Leon AC, Keller MB, et al. Recurrence after recovery from major depressive disorder during 15 years of observational follow-up. American Journal of Psychiatry, 1999;156(7):1000–1006. Source for the name of the NIMH Collaborative Program on the Psychobiology of Depression. doi.org
Sullivan PF, Neale MC, Kendler KS. Genetic epidemiology of major depression: review and meta-analysis. American Journal of Psychiatry, 2000;157(10):1552–1562. Source for heritability of 37% (likely range 31% to 42%, probably a lower bound), the near-zero shared environment, the individual environment with measurement error, and depression resulting from both genes and environment. doi.org
Kendler KS, Gatz M, Gardner CO, Pedersen NL. A Swedish national twin study of lifetime major depression. American Journal of Psychiatry, 2006;163(1):109–114. Source for heritability of 42% in women and 29% in men. doi.org
Wray NR, Ripke S, Mattheisen M, et al. Genome-wide association analyses identify 44 risk variants and refine the genetic architecture of major depression. Nature Genetics, 2018;50(5):668–681. Source for the 44 variants, the 9% of the variation in liability from common variants, and the genetic risk score ranking a case above a control 57% of the time. pmc.ncbi.nlm.nih.gov
Howard DM, Adams MJ, Clarke TK, et al. Genome-wide meta-analysis of depression identifies 102 independent variants and highlights the importance of the prefrontal brain regions. Nature Neuroscience, 2019;22(3):343–352. Source for the 102 variants. pmc.ncbi.nlm.nih.gov
Caspi A, Sugden K, Moffitt TE, et al. Influence of life stress on depression: moderation by a polymorphism in the 5-HTT gene. Science, 2003;301(5631):386–389. Source for the 2003 finding on the short version of 5-HTTLPR and stressful life events. doi.org
Culverhouse RC, Saccone NL, Horton AC, et al. Collaborative meta-analysis finds no evidence of a strong interaction between stress and 5-HTTLPR genotype contributing to the development of depression. Molecular Psychiatry, 2018;23(1):133–142. Source for the test in 38,802 people and its result. pmc.ncbi.nlm.nih.gov
Border R, Johnson EC, Evans LM, et al. No support for historical candidate gene or candidate gene-by-interaction hypotheses for major depression across multiple large samples. American Journal of Psychiatry, 2019;176(5):376–387. Source for the eighteen candidate genes tested in samples of 62,138 to 443,264 people, and the authors' conclusion. pmc.ncbi.nlm.nih.gov
Moncrieff J, Cooper RE, Stockmann T, et al. The serotonin theory of depression: a systematic umbrella review of the evidence. Molecular Psychiatry, 2023;28(8):3243–3256 (online July 2022). Source for the six areas of research and the review's conclusion. doi.org
Jauhar S, Arnone D, Baldwin DS, et al. A leaky umbrella has little value: evidence clearly indicates the serotonin system is implicated in depression. Molecular Psychiatry, 2023;28(8):3149–3152. Source for the reply's 35 authors, its view that the conclusion was overstated, and two of its criticisms. pmc.ncbi.nlm.nih.gov
Moncrieff J, Cooper RE, Stockmann T, et al. The serotonin hypothesis of depression: both long discarded and still supported? Molecular Psychiatry, 2023;28(8):3160–3163. Source for the authors' answer to their critics. doi.org
Kendler KS, Karkowski LM, Prescott CA. Causal relationship between stressful life events and the onset of major depression. American Journal of Psychiatry, 1999;156(6):837–841. Source for the odds ratio of 3.58 within identical twin pairs, and the share of the link the authors judged non-causal. doi.org
University of Essex. Oration for Professor George Brown, honorary graduate, 2002. Source for Brown and Harris's Camberwell findings on class, life events and vulnerability factors. www1.essex.ac.uk
Costello CG. Social factors associated with depression: a retrospective community study. Psychological Medicine, 1982;12(2):329–339. Source for the Calgary replication and its findings. doi.org
Ekers D, Webster L, Van Straten A, Cuijpers P, Richards D, Gilbody S. Behavioural activation for depression; an update of meta-analysis of effectiveness and sub group analysis. PLoS One, 2014;9(6):e100100. Source for what behavioural activation is. pmc.ncbi.nlm.nih.gov
Cuijpers P, Ciharova M, Tong L, et al. Behavioral activation for depression: a comprehensive systematic review and meta-analysis. Clinical Psychology Review, 2026;128:102783. Source for the 105 trials and 13,933 patients, the standardised mean difference of 0.67 against controls, the result at 12 months, the comparison with other therapies, the heterogeneity and prediction interval, and the 0.36 for self-guided behavioural activation. doi.org
Cipriani A, Furukawa TA, Salanti G, et al. Comparative efficacy and acceptability of 21 antidepressant drugs for the acute treatment of adults with major depressive disorder: a systematic review and network meta-analysis. The Lancet, 2018;391(10128):1357–1366. Source for the 522 trials and 116,477 participants, all 21 drugs beating placebo, the odds ratios for response of 2.13 and 1.37, the standardised mean difference of 0.30, the risk-of-bias shares and the certainty of the evidence. pmc.ncbi.nlm.nih.gov
Kirsch I, Deacon BJ, Huedo-Medina TB, Scoboria A, Moore TJ, Johnson BT. Initial severity and antidepressant benefits: a meta-analysis of data submitted to the Food and Drug Administration. PLoS Medicine, 2008;5(2):e45. Source for the FDA data on four newer antidepressants, the improvements of 9.6 and 7.8 points and the difference of 1.8, the standardised difference of 0.32, and NICE's criterion of 3 points or a standardised mean difference of 0.50. pmc.ncbi.nlm.nih.gov
Fountoulakis KN, Möller HJ. Efficacy of antidepressants: a re-analysis and re-interpretation of the Kirsch data. International Journal of Neuropsychopharmacology, 2011;14(3):405–412. Source for the recalculated difference of 2.18 or 2.68 points, and venlafaxine and paroxetine above 3. doi.org
Huedo-Medina TB, Johnson BT, Kirsch I. Kirsch et al.'s (2008) calculations are correct: reconsidering Fountoulakis & Möller's re-analysis of the Kirsch data. International Journal of Neuropsychopharmacology, 2012;15(8):1193–1198. Source for the reply that the reanalysis weighted the trials wrongly, that no single drug reached NICE's criterion when calculated correctly, and that the reanalysis found the same standardised effect size. doi.org
Turner EH, Matthews AM, Linardatos E, Tell RA, Rosenthal R. Selective publication of antidepressant trials and its influence on apparent efficacy. New England Journal of Medicine, 2008;358(3):252–260. Source for the 74 trials registered with the FDA, the 31% unpublished, and 94% positive in print against 51% by the FDA's reading. doi.org
Turner EH, Cipriani A, Furukawa TA, Salanti G, de Vries YA. Selective publication of antidepressant trials and its influence on apparent efficacy: updated comparisons and meta-analyses of newer versus older trials. PLoS Medicine, 2022;19(1):e1003886. Source for the effect sizes of 0.41 in the journals and 0.31 in the FDA's data for all 74 trials, published and unpublished. pmc.ncbi.nlm.nih.gov
Rush AJ, Trivedi MH, Wisniewski SR, et al. Acute and longer-term outcomes in depressed outpatients requiring one or several treatment steps: a STAR*D report. American Journal of Psychiatry, 2006;163(11):1905–1917. Source for the 67% cumulative remission after up to four steps, on the self-report scale. doi.org
Pigott HE, Kim T, Xu C, Kirsch I, Amsterdam J. What are the treatment remission, response and extent of improvement rates after up to four trials of antidepressant therapies in real-world depressed patients? A reanalysis of the STAR*D study's patient-level data with fidelity to the original research protocol. BMJ Open, 2023;13(7):e063095. Source for the 67% as a theoretical figure, the 53.7% of its reanalysed patients who dropped out, the protocol's blinded Hamilton scale and where the protocol was silent, the patients the reanalysis excluded, the 35.0% and 41.3%, and the absence of a placebo group. pmc.ncbi.nlm.nih.gov
Rush AJ, Trivedi MH, Fava M, et al. Rejecting the accusation of a violated STAR*D protocol. Psychiatric Times, 7 March 2024; the same authors' reply in the American Journal of Psychiatry is The STAR*D data remain strong: reply to Pigott et al., 2023;180(12):919–920. Source for the 941 patients the reanalysis dropped, the authors' view that excluding hundreds with low symptom scores most likely explains the difference, and the separate study, co-authored by Pigott's senior author, that found 60% remission over 12 months. psychiatrictimes.com
Sakurai H, Noma H, Watanabe K, Uchida H, Furukawa TA. Cumulative remission rate after sequential treatments in depression: reappraisal of the STAR*D trial data. World Psychiatry, 2024;23(1):156–157. Source for the weighted estimates of 53.8%, 74.5% and 87.5% at 90 days, six months and a year, on the self-report scale. pmc.ncbi.nlm.nih.gov
Cuijpers P, Smit F, Bohlmeijer E, Hollon SD, Andersson G. Efficacy of cognitive-behavioural therapy and other psychological treatments for adult depression: meta-analytic study of publication bias. British Journal of Psychiatry, 2010;196(3):173–178. Source for the effect of 0.67, falling to 0.42 after adjustment for publication bias. doi.org
Cuijpers P, Karyotaki E, Reijnders M, Ebert DD. Was Eysenck right after all? A reassessment of the effects of psychotherapy for adult depression. Epidemiology and Psychiatric Sciences, 2019;28(1):21–30. Source for the unadjusted 0.70, the adjusted 0.31, and the 23% of studies at low risk of bias. pmc.ncbi.nlm.nih.gov
Munder T, Flückiger C, Leichsenring F, et al. Is psychotherapy effective? A re-analysis of treatments for depression. Epidemiology and Psychiatric Sciences, 2019;28(3):268–274. Source for the reanalysis by nine authors, its treatment of waiting lists and outliers, and its effects of about 0.70 against waiting lists and 0.31 against usual care. pmc.ncbi.nlm.nih.gov
Cuijpers P, Karyotaki E, Reijnders M, Ebert DD. Is psychotherapy effective? Pretending everything is fine will not help the field forward. Epidemiology and Psychiatric Sciences, 2019;28(3):356–357. Source for Cuijpers's reply. pmc.ncbi.nlm.nih.gov
Cuijpers P, Quero S, Noma H, et al. Psychotherapies for depression: a network meta-analysis covering efficacy, acceptability and long-term outcomes of all main treatment types. World Psychiatry, 2021;20(2):283–293. Source for the 331 trials and the therapies not differing significantly, except non-directive supportive counselling. pmc.ncbi.nlm.nih.gov
Noetel M, Sanders T, Gallardo-Gómez D, et al. Effect of exercise for depression: systematic review and network meta-analysis of randomised controlled trials. BMJ, 2024;384:e075847. Source for the 218 studies, 495 arms and 14,170 participants, the effects against active controls, the 107 participants behind the dance figure, the one study at low risk of bias, the confidence ratings and the authors' conclusion. pmc.ncbi.nlm.nih.gov
Davies J, Read J. A systematic review into the incidence, severity and duration of antidepressant withdrawal effects: are guidelines evidence-based? Addictive Behaviors, 2019;97:111–121. Source for the weighted average of 56%, the range of 27% to 86%, and the 46% choosing the most severe rating in four large studies. doi.org
Jauhar S, Hayes J, Goodwin GM, Baldwin DS, Cowen PJ, Nutt DJ. Antidepressants, withdrawal, and addiction; where are we now? Journal of Psychopharmacology, 2019;33(6):655–659. Source for the criticism of the convenience-sample surveys. pmc.ncbi.nlm.nih.gov
Henssler J, Schmidt Y, Schmidt U, et al. Incidence of antidepressant discontinuation symptoms: a systematic review and meta-analysis. The Lancet Psychiatry, 2024;11(7):526–535. Source for the 79 studies, at least one symptom in 31% after stopping an antidepressant against 17% after stopping a placebo, and severe symptoms in 2.8% against 0.6%. doi.org
Royal College of Psychiatrists. RCPsych calls on NICE to update its antidepressant withdrawal advice. Press release, 29 May 2019. Source for the College's statement on severe and long-lasting withdrawal, and NICE's earlier advice of four weeks. rcpsych.ac.uk
National Institute for Health and Care Excellence. Depression in adults, quality standard QS8, statement 4: Stopping antidepressants. Last updated 29 June 2023. Source for reducing the dose in stages. nice.org.uk
Olfson M, Marcus SC, Druss B, Elinson L, Tanielian T, Pincus HA. National trends in the outpatient treatment of depression. JAMA, 2002;287(2):203–209. Source for outpatient treatment of 0.73 people in every 100 in 1987 and 2.33 in 1997. rand.org
Marcus SC, Olfson M. National trends in the treatment for depression from 1998 to 2007. Archives of General Psychiatry, 2010;67(12):1265–1273. Source for 2.88 people in every 100 in 2007. doi.org
Ormel J. [More treatment but no less depression. An uncomfortable paradox] (in Dutch, with an English abstract). Tijdschrift voor Psychiatrie, 2023;65(8):484–490. Source for chronic and recurrent cases accounting for most prevalence. pubmed.ncbi.nlm.nih.gov
Mulder RT, Jorm AF. The impact of antidepressants and human development measures on the prevalence of sadness, worry and unhappiness: cross-national comparison. BJPsych Open, 2023;9:e182. Source for antidepressant prescribing against sadness, worry and unhappiness across OECD countries, and the Human Development Index's association with less of all three. pmc.ncbi.nlm.nih.gov
Supporting someone. The carer guidance and its evidence base are set out with their sources on the companion page, How to Help Someone With Depression.
Crisis lines. Numbers, text codes and opening hours as each service or health body published them in October 2026: 988 Lifeline 988lifeline.org and its languages page 988lifeline.org; SAMHSA on calling 911 samhsa.gov; Crisis Text Line crisistextline.org; Samaritans samaritans.org, its Welsh Language Line samaritans.org, its retired text service samaritans.org and its change for withheld numbers in Ireland samaritans.org; Shout giveusashout.org; CALM thecalmzone.net; NHS England nhs.uk, NHS inform for Scotland nhsinform.scot and Hywel Dda University Health Board for NHS 111 Wales hduhb.nhs.wales; the Government of Ireland on 112 and 999 gov.ie. PAPYRUS: the joint administrators' notice of 7 September 2026 opusllp.com, and two council directories that still list HOPELINE247 scotborders.gov.uk westnorthants.gov.uk.
Cite this article
TruthBased.org. “What Is Depression?” Updated October 2026. https://www.truthbased.org/what-is-depression