Health & Medicine
Can Sociopaths Be Fixed?
What treatment has been tried, and why nobody yet knows whether it works.
Health & Medicine
What Is Depression?
What the diagnosis requires, how dangerous depression is, and how much treatment helps.
Health & Medicine
How to Help Someone With Depression
Advice for families and friends, and which of it has been tested.
What Exactly Creates a Sociopath?
Sociopathy is blamed on a warrior gene, on an abusive childhood or on a damaged brain. This page sets each explanation against what twin studies, genetic studies, maltreatment research and brain imaging measured.
Jump to the verdict ↓
Before the evidence
None of the studies below measures "sociopathy." They measure antisocial personality disorder, psychopathy, conduct disorder, or antisocial behaviour, and these are four different things. Every figure below is labelled with what it actually measured. Whether anything can treat the condition is a separate question, covered in Can Sociopaths Be Fixed?
The short answer
No single cause. Antisocial personality disorder (ASPD), the diagnosis behind the word sociopath, has several known influences and no known single cause. In twin studies, genes account for 38% to 51% of the differences between people in antisocial behaviour and ASPD, spread across many variants of small effect. Childhood maltreatment goes with nearly twice the odds of antisocial behaviour in adulthood, compared with peers who were not maltreated. But twin studies disagree on how much of that is cause.
What the word sociopath refers to
Sociopathy is not a diagnosis in today's psychiatric manual, the Diagnostic and Statistical Manual of Mental Disorders (DSM). The manual's first edition, in 1952, did list a "sociopathic personality disturbance", one form of which was the "antisocial reaction". The words sociopath and psychopath were often used interchangeably.
The diagnosis the word maps to is antisocial personality disorder (ASPD). The current manual, DSM-5-TR, requires a pervasive pattern of disregard for and violation of the rights of others since age 15. The pattern must show in at least three of seven ways: repeated unlawful behaviour, deceitfulness, impulsivity, irritability and aggressiveness, reckless disregard for safety, consistent irresponsibility, and lack of remorse. The person must be at least 18, with evidence of conduct disorder that began before age 15. The criteria are mainly about behaviour, such as crime and irresponsibility.
In the United States, 4.3% of adults have had ASPD at some point in their lives, according to the National Epidemiologic Survey on Alcohol and Related Conditions (NESARC-III). It interviewed 36,309 adults face to face in 2012 and 2013. The rate was 6.4% among men and 2.4% among women.
The survey's authors note that 4.3% falls within the 3% to 5% of earlier US surveys. Because the survey covered households and some group quarters, not prisons, they think it likely underestimates. A Cochrane review of psychological treatments for ASPD says most studies put it at 2% to 3% of the general population.
Conduct disorder is the childhood diagnosis, and ASPD cannot be diagnosed without evidence of it before age 15. Most children with conduct disorder do not go on to develop ASPD. StatPearls, a clinical reference, says nearly 25% of girls and 40% of boys diagnosed with conduct disorder eventually do.
NESARC-III, which asked adults about their childhood, gives a much higher figure. In that 2012-13 survey, 1,600 respondents met the ASPD criteria. Only 154 had conduct disorder without going on to ASPD. So about nine in ten of the adults who recalled conduct disorder also met the adult criteria.
Psychopathy is a related construct, measured with the Hare Psychopathy Checklist-Revised rather than diagnosed from the DSM. It adds interpersonal and emotional traits, such as a lack of empathy, grandiosity and shallow affect, to the behaviour that ASPD describes. The overlap runs one way. Most people who meet the criteria for psychopathy also meet those for ASPD, but most people with ASPD do not meet the criteria for psychopathy.
The popular split, that psychopaths are born and sociopaths are made, has a scholarly version in the psychologist David Lykken's 1995 book The Antisocial Personalities. His publisher's summary describes sociopaths as people whose failure of socialization "can be attributed largely to incompetent or indifferent rearing". It says fearlessness, one of the heritable traits the book reviews, seems to be one basis for primary psychopathy.
As a division of causes, the split does not fit the evidence. A 2018 review of 24 studies found psychopathic traits modestly to highly heritable. A 2022 meta-analysis of 47 studies found a moderate link between psychopathy and childhood physical abuse, emotional abuse and neglect. Antisocial behaviour, as the sections below show, is also partly heritable and also linked to maltreatment.
Heritability
Twin and adoption studies find a moderate genetic contribution to antisocial behaviour. A 2002 meta-analysis by Rhee and Waldman pooled 51 twin and adoption studies. Its best-fitting model divided the variation between people as the table shows.
| Influence | Share of the variation |
|---|---|
| Additive genetic influences | 32% |
| Nonadditive genetic influences | 9% |
| All genetic influences, the two above together | 41% |
| Shared environment | 16% |
| Nonshared environment, the experiences unique to each person | 43% |
Twin studies of antisocial personality disorder (ASPD) itself give figures in the same range. A 2017 study interviewed 2,794 Norwegian twins with a structured diagnostic interview. The single factor that the seven ASPD criteria share had a heritability of 51%. Its 95% confidence interval ran from 40% to 67%. An earlier study of the same Norwegian twin panel found a heritability of 38% for ASPD traits.
Heritability describes variation within a population, not a share of any one person. A heritability of 51% does not mean genes caused half of anyone's condition. It means that in the population studied, about half the variation between people was due to genetic differences.
In both studies, experiences unique to each person accounted for about as much of the variation as genes did. In Rhee and Waldman's meta-analysis that was 43% against 41%. In the Norwegian twins it was 49% against 51%, and that share also takes in measurement error.
Studies of DNA itself find much smaller figures. A 2022 genome-wide study by Tielbeek and colleagues pooled 85,359 people from 28 samples. It found one region linked to antisocial behaviour, in an intron of the FOXP2 gene. All the common variants it measured explained 3.4% of the variation in the data of the study's own consortium and 7.7% in its combined analysis. In a separate set comparing people diagnosed with disruptive behaviour disorders with controls, the estimate was 24.8%.
The authors describe antisocial behaviour as highly polygenic. Each variant that contributes has a small effect, so a score built from all of them still explains only a small share of antisocial behaviour.
The warrior gene
On its own, variation in the monoamine oxidase A (MAOA) gene, nicknamed the "warrior gene", has only a modest link with antisocial behaviour. The gene makes an enzyme that breaks down the neurotransmitters dopamine, norepinephrine and serotonin. A common variant in the gene's promoter region lowers the enzyme's activity. This low-activity variant is the one studied in connection with antisocial behaviour.
A 2014 meta-analysis by Ficks and Waldman found the gene's promoter variants significantly associated with antisocial behaviour across studies. But the size of the association varied widely between studies, and the authors called the role of such common variants modest. The low-activity variant is common: 37% of the males in the original 2002 study of the variant and childhood maltreatment carried it.
What the research supports is narrower and more conditional: in males, a common gene variant appears to change how much harm childhood maltreatment does. The 2002 study, by Caspi and colleagues, followed 442 males of a New Zealand birth cohort, the Dunedin study, to age 26. Childhood maltreatment predicted antisocial outcomes more strongly among those with the low-activity variant. In that study the variant had no effect by itself.
Only 12% of the male cohort had both the low-activity variant and a history of maltreatment. Those males accounted for 44% of the cohort's violent convictions. Among the severely maltreated boys who carried the low-activity variant, 85% developed some form of antisocial behaviour.
A 2014 meta-analysis by Byrd and Manuck tested this across 20 male cohorts and confirmed it. Early adversity predicted antisocial outcomes more strongly for the low-activity variant, and the effect was specific to maltreatment rather than adversity in general. Across 11 female cohorts, the variant did not change the effect of early adversity as a whole. For maltreatment alone, a weak effect ran the other way, stronger in women with the high-activity variant. In women, the pattern has not been established.
Single studies agree only partly. Byrd and Manuck pooled 12 later studies of maltreatment in men. Of those, 6 found the effect at the usual level of significance, a one-tailed p value below .05. Studies of this kind, testing one candidate gene against one environment, replicate poorly as a field. A 2011 review of the first decade of such research in psychiatry found 96% of first studies significant, against 27% of the attempts to replicate them.
Download this conclusion: the warrior gene

This section's finding as one image. Its bars show the 2002 study's figures. Males with both the low-activity variant and a history of maltreatment were 12% of the male cohort, and accounted for 44% of its violent convictions. The image is 1,080 by 1,350 pixels, and anyone may download it and post it.
Childhood maltreatment and other early factors
Childhood maltreatment has a measured but modest link with later antisocial behaviour. A 2018 meta-analysis by Braga, Cunha and Maia pooled 14 prospective studies of 20,946 people followed into adulthood. Compared with peers who were not maltreated, maltreated young people had nearly twice the odds of antisocial behaviour as adults, an odds ratio of 1.96. The 95% confidence interval ran from 1.42 to 2.71.
For later violence, a 2020 meta-analysis by Fitton, Yu and Fazel found an odds ratio of 1.8 and called the increase in risk modest. It pooled 18 prospective studies of 39,271 people.
Prospective studies follow people forward from childhood, but they cannot by themselves separate the effect of maltreatment from what a family passes on. Twin studies try to, and they disagree. A Swedish study of 18,083 adult twins compared those who reported maltreatment with unrelated people. Twins who reported maltreatment had nearly twice the odds of a violent conviction (odds ratio 1.98). Compared with their own twin who had not been maltreated, the odds ratio fell to 1.18, which was not statistically significant.
The Swedish authors concluded that maltreatment was a weak causal risk factor for adult violent offending, with substantial confounding by genes or family environment. A study of 1,116 twin pairs at ages 5 and 7 pointed the other way. It found that physical maltreatment appeared to play a causal role in children's antisocial behaviour.
For antisocial personality disorder (ASPD) itself, as opposed to antisocial behaviour, the evidence is thinner. A 2021 umbrella review by Solmi and colleagues found only five meta-analyses of risk factors for personality disorders that met its criteria. No risk factor for ASPD had evidence of class I, II or III, its strongest grades; six met class IV. That does not mean maltreatment is irrelevant, since the meta-analyses of antisocial behaviour above find a link.
Smoking in pregnancy shows how hard such causes are to pin down. A 2006 meta-analysis found its link with children's later deviant or criminal behaviour statistically significant but small, and sensitive to how studies were done. A 2013 study using adoption and in vitro fertilisation (IVF) designs found the link with conduct problems held even among children reared by mothers genetically unrelated to them. A 2022 review said findings on conduct disorder need more research using genetically sensitive designs.
Other features of family life are linked too. Erratic, coercive and punitive parenting puts boys at risk of conduct disorder, antisocial personality symptoms and violent offending, as Caspi and colleagues summarised the earlier research.
Twin studies also separate the environment that siblings share from experiences that differ between them. The shared environment shows up in conduct disorder: a 2013 study of 2,769 male twins in Virginia found one shared-environment factor, linked to covert acts such as stealing. In the Norwegian twin studies of adult ASPD it did not show up at all, and the environment's share came entirely from experiences that differ between twins.
The brain
Imaging studies find differences between groups. A 2009 meta-analysis by Yang and Raine pooled 43 structural and functional imaging studies of antisocial, violent and psychopathic individuals. It found reduced prefrontal structure and function, with an overall effect size (Cohen's d) of -0.60. The differences were localised to the right orbitofrontal cortex, the right anterior cingulate cortex and the left dorsolateral prefrontal cortex.
A 2023 meta-analysis by Tully and colleagues pooled 23 studies of young people with disruptive behaviour disorders and adults with antisocial personality disorder (ASPD) or psychopathy. Compared with healthy controls, these groups had smaller total grey matter (an effect size of -0.6) and smaller amygdalas (-0.89).
None of this establishes a cause. The studies compare groups at one point in time, so they cannot show whether a brain difference came before the behaviour or after it. Yang and Raine wrote that their meta-analysis "underscores the critical need for longitudinal imaging studies".
Substance use is one possible explanation. In the National Epidemiologic Survey on Alcohol and Related Conditions (NESARC-III), 83.6% of adults with ASPD had had a substance use disorder, against 32.5% of adults with no antisocial syndrome. A 2019 pooled analysis of 3,240 people linked dependence on any of five substances to lower volume or thickness in regions including the medial orbitofrontal cortex. But Yang and Raine found that the prefrontal effect did not differ significantly between studies with and without comorbid disorders such as substance abuse.
The samples are small and mixed. Yang and Raine's 43 studies held 789 antisocial individuals between them. Of those individuals, 83.9% were male. Each meta-analysis pools several groups under one label.
Tully and colleagues also found total grey matter more variable in the antisocial groups than in controls. They say the finding suggests a key role for this variability in how these disorders diverge.
The verdict: what the evidence shows
No single cause has been found. Genes, childhood experience and the brain all show up in the evidence on antisocial behaviour and on antisocial personality disorder (ASPD), the diagnosis behind the word sociopath. None has been shown to produce it alone.
The genetic part is real but spread across many genes: twin studies trace 38% to 51% of the differences between people to genes, and no single gene explains them. Childhood maltreatment goes with nearly twice the odds of antisocial behaviour in adulthood, compared with peers who were not maltreated. But twin studies disagree on how much of that link is cause. The brain differences come from comparing groups at one point in time, which cannot show which came first.
Five claims, against the evidence
Claim"Psychopaths are born, sociopaths are made."
Not supportedLike antisocial behaviour, psychopathy is linked to both genes and childhood maltreatment. A 2018 review of 24 studies found psychopathic traits modestly to highly heritable, and a 2022 meta-analysis linked psychopathy to childhood abuse and neglect.
Claim"It's in the genes."
PartlyTwin studies trace 38% to 51% of the differences between people in antisocial behaviour and antisocial personality disorder (ASPD) to genes. But a 2022 genome-wide study of 85,359 people found only one linked region, and many variants each with a small effect.
Claim"A 'warrior gene' causes violence."
Not shownOn its own, variation in the monoamine oxidase A (MAOA) gene has only a modest link with antisocial behaviour. In males, its low-activity variant appears to change how much harm childhood maltreatment does, a finding later single studies support only in part.
Claim"Childhood abuse causes it."
Partly supportedIn prospective studies, maltreated young people had nearly twice the odds of antisocial behaviour as adults, compared with peers who were not maltreated (odds ratio 1.96). Twin studies disagree on how much of that link is cause rather than family background.
Claim"Sociopaths have damaged brains."
Correlation onlyOn average, antisocial groups show reduced prefrontal structure and function, and smaller amygdalas, than controls. The studies compare groups at one point in time, so they cannot show which came first.
Download the conclusion
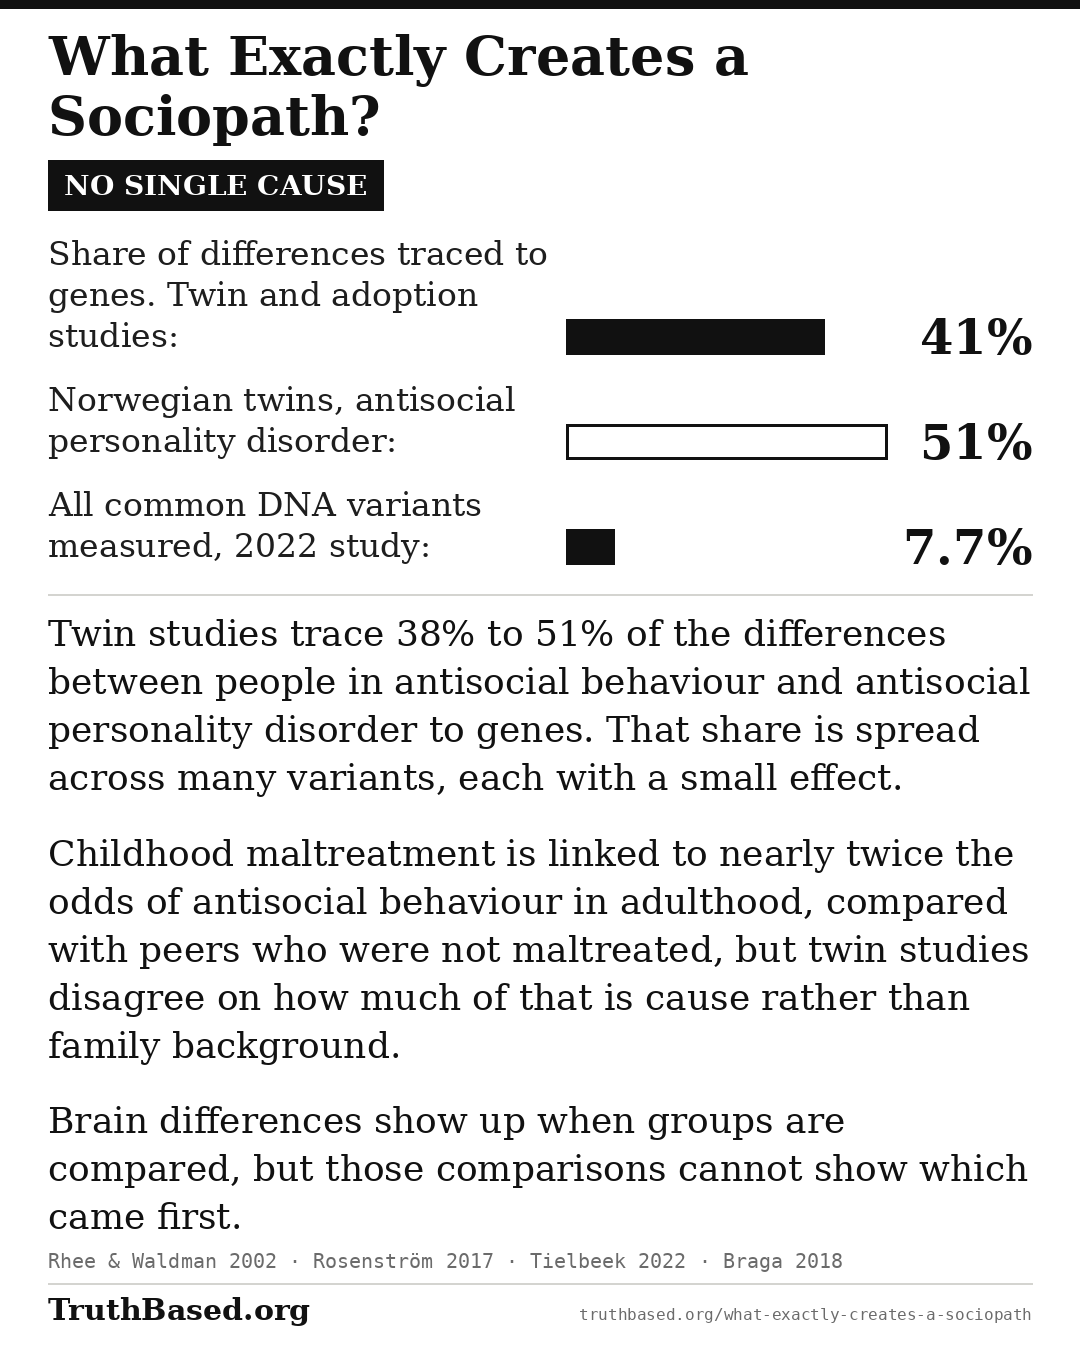
The verdict above as one image. Its bars show the share of the differences between people traced to genes. It was 41% for antisocial behaviour in twin and adoption studies, and 51% for antisocial personality disorder in Norwegian twins. For all the common DNA variants measured in a 2022 genome-wide study, the share was 7.7%. The image is 1,080 by 1,350 pixels, and anyone may download it and post it.
What would change this conclusion
This article concludes that:
- twin studies trace 38% to 51% of the differences between people in antisocial behaviour and antisocial personality disorder to genes, spread across many variants with no single gene behind them;
- childhood maltreatment goes with nearly twice the odds of antisocial behaviour in adulthood, compared with peers not maltreated, but twin studies disagree on how much of that link is cause;
- the brain differences found in antisocial groups have not been shown to come before the behaviour.
These conclusions would be falsified by:
• A genome-wide study that finds one variant, or a few, accounting for most of the genetic share that twin studies find
• Large twin or sibling studies of adult antisocial behaviour that agree on whether maltreatment's link survives comparison within families
• Longitudinal imaging studies that scan children before antisocial behaviour begins and find that the brain differences come first
Sources
Crego C, Widiger TA. Psychopathy and the DSM. Journal of Personality, 2015;83(6). Source for the first edition of the DSM, in 1952, listing a "sociopathic personality disturbance", one variation of which was the "antisocial reaction". doi.org
Torrico TJ, Hany M. Antisocial Personality Disorder. StatPearls, NCBI Bookshelf, last updated 17 June 2026. Source for the DSM-5-TR criteria for antisocial personality disorder, which the chapter reproduces; the words psychopath and sociopath being often used interchangeably; the criteria being mainly about behaviour; the one-way overlap between psychopathy and ASPD; and most children with conduct disorder not developing ASPD, with nearly 25% of girls and 40% of boys who do. ncbi.nlm.nih.gov
Goldstein RB, Chou SP, Saha TD, et al. The epidemiology of antisocial behavioral syndromes in adulthood: results from the National Epidemiologic Survey on Alcohol and Related Conditions-III. Journal of Clinical Psychiatry, 2017;78(1):90–98. Source for the lifetime ASPD prevalence of 4.3% among 36,309 adults interviewed in 2012 and 2013, 6.4% of men and 2.4% of women; the 3% to 5% of earlier US surveys; the authors' view that the figure likely underestimates; the 1,600 respondents with ASPD and 154 with conduct disorder who did not go on to it; and the 83.6% of adults with ASPD who had had a substance use disorder, against 32.5% of adults with no antisocial syndrome. pmc.ncbi.nlm.nih.gov
Gibbon S, Khalifa NR, Cheung NH, Völlm BA, McCarthy L. Psychological interventions for antisocial personality disorder. Cochrane Database of Systematic Reviews, 2020, Issue 9, CD007668. Source for most studies putting the prevalence of ASPD at 2% to 3% of the general population. pmc.ncbi.nlm.nih.gov
Lykken DT. The Antisocial Personalities. Hillsdale, NJ: Erlbaum, 1995. Source, through its publisher's description, for sociopaths as people whose failure of socialization can be attributed largely to incompetent or indifferent rearing, and for fearlessness as seemingly one basis for primary psychopathy. routledge.com
Dhanani S, Kumari V, Puri BK, Treasaden I, Young S, Sen P. A systematic review of the heritability of specific psychopathic traits using Hare's two-factor model of psychopathy. CNS Spectrums, 2018;23(1):29–38. Source for the 24 studies and the modest to high heritability of psychopathic traits. doi.org
de Ruiter C, Burghart M, De Silva R, Griesbeck Garcia S, Mian U, Walshe E, Zouharova V. A meta-analysis of childhood maltreatment in relation to psychopathic traits. PLoS One, 2022;17(8):e0272704. Source for the 47 studies and the moderate link between psychopathy and childhood physical abuse, emotional abuse and neglect. pmc.ncbi.nlm.nih.gov
Rhee SH, Waldman ID. Genetic and environmental influences on antisocial behavior: a meta-analysis of twin and adoption studies. Psychological Bulletin, 2002;128(3):490–529. Source for the 51 twin and adoption studies and the shares of variation in antisocial behaviour in the best-fitting model: additive genetic 32%, nonadditive genetic 9%, shared environment 16% and nonshared environment 43%. doi.org
Rosenström T, Ystrom E, Torvik FA, et al. Genetic and environmental structure of DSM-IV criteria for antisocial personality disorder: a twin study. Behavior Genetics, 2017;47(3):265–277. Source for the 2,794 Norwegian twins, the heritability of 51% (95% confidence interval 40% to 67%) of the factor the ASPD criteria share, the 49% from non-shared environment, which includes measurement error, and the absence of shared environmental effects. pmc.ncbi.nlm.nih.gov
Torgersen S, Czajkowski N, Jacobson K, et al. Dimensional representations of DSM-IV cluster B personality disorders in a population-based sample of Norwegian twins: a multivariate study. Psychological Medicine, 2008;38(11):1617–1625. Source for the heritability of 38% for ASPD traits in the same Norwegian twin panel. doi.org
MedlinePlus Genetics, US National Library of Medicine. What is heritability? Source for what a heritability figure does and does not mean. medlineplus.gov
Tielbeek JJ, Uffelmann E, Williams BS, et al. Uncovering the genetic architecture of broad antisocial behavior through a genome-wide association study meta-analysis. Molecular Psychiatry, 2022;27(11):4453–4463. Source for the 85,359 people from 28 samples, the one region linked to antisocial behaviour in an intron of FOXP2, the share of variation explained by common variants (3.4%, 7.7% and 24.8%), and the highly polygenic picture. pmc.ncbi.nlm.nih.gov
Oliva A, Grassi S, Zedda M, Molinari M, Ferracuti S. Forensic value of genetic variants associated with anti-social behavior. Diagnostics, 2021;11(12):2386. Source for MAOA's nickname, the "warrior gene", and the enzyme's breakdown of dopamine, norepinephrine and serotonin. pmc.ncbi.nlm.nih.gov
Ficks CA, Waldman ID. Candidate genes for aggression and antisocial behavior: a meta-analysis of association studies of the 5HTTLPR and MAOA-uVNTR. Behavior Genetics, 2014;44(5):427–444. Source for the significant association of the MAOA promoter variants with antisocial behaviour across studies, its wide variation between studies, and the authors' word modest. doi.org
Caspi A, McClay J, Moffitt TE, Mill J, Martin J, Craig IW, Taylor A, Poulton R. Role of genotype in the cycle of violence in maltreated children. Science, 2002;297(5582):851–854. Source for the Dunedin birth cohort followed to age 26, the 37% of males carrying the low-activity variant, maltreatment's stronger effect among them, the variant's lack of an effect by itself, the 12% of the male cohort and 44% of its violent convictions, the 85% of severely maltreated low-activity boys who developed some antisocial behaviour, and the earlier research on erratic, coercive and punitive parenting. doi.org dunedinstudy.otago.ac.nz
Byrd AL, Manuck SB. MAOA, childhood maltreatment, and antisocial behavior: meta-analysis of a gene-environment interaction. Biological Psychiatry, 2014;75(1):9–17. Source for the 20 male cohorts, the effect's specificity to maltreatment, the 11 female cohorts, the 442 males of the 2002 study, and the one-tailed p values of the 12 later studies of maltreatment in men, 6 of them below .05. pubmed.ncbi.nlm.nih.gov moffittcaspi.trinity.duke.edu
Duncan LE, Keller MC. A critical review of the first 10 years of candidate gene-by-environment interaction research in psychiatry. American Journal of Psychiatry, 2011;168(10):1041–1049. Source for 96% of first studies being significant, against 27% of the attempts to replicate them. pmc.ncbi.nlm.nih.gov
Braga T, Cunha O, Maia A. The enduring effect of maltreatment on antisocial behavior: a meta-analysis of longitudinal studies. Aggression and Violent Behavior, 2018. Source for the 14 prospective studies of 20,946 people followed into adulthood and the odds ratio of 1.96 (95% confidence interval 1.42 to 2.71). doi.org cipsi.uminho.pt
Fitton L, Yu R, Fazel S. Childhood maltreatment and violent outcomes: a systematic review and meta-analysis of prospective studies. Trauma, Violence, & Abuse, 2020;21(4):754–768. Source for the 18 prospective studies of 39,271 people, the odds ratio of 1.8 for later violence (95% confidence interval 1.4 to 2.3), and the authors' description of the increase in risk as modest. doi.org
Forsman M, Långström N. Child maltreatment and adult violent offending: population-based twin study addressing the 'cycle of violence' hypothesis. Psychological Medicine, 2012;42(9):1977–1983. Source for the 18,083 Swedish twins, the odds ratios of 1.98 against unrelated people and 1.18 against co-twins, and the authors' conclusion. doi.org
Jaffee SR, Caspi A, Moffitt TE, Taylor A. Physical maltreatment victim to antisocial child: evidence of an environmentally mediated process. Journal of Abnormal Psychology, 2004;113(1):44–55. Source for the 1,116 twin pairs at ages 5 and 7 and the finding that physical maltreatment played a causal role in children's antisocial behaviour. doi.org
Solmi M, Dragioti E, Croatto G, et al. Risk and protective factors for personality disorders: an umbrella review of published meta-analyses of case-control and cohort studies. Frontiers in Psychiatry, 2021;12:679379. Source for the five eligible meta-analyses and the finding that no risk factor for ASPD had evidence of class I, II or III, with six at class IV. pmc.ncbi.nlm.nih.gov
Pratt TC, McGloin JM, Fearn NE. Maternal cigarette smoking during pregnancy and criminal/deviant behavior: a meta-analysis. International Journal of Offender Therapy and Comparative Criminology, 2006;50(6):672–690. Source for the statistically significant but small link, sensitive to how studies were done. doi.org
Gaysina D, Fergusson DM, Leve LD, et al. Maternal smoking during pregnancy and offspring conduct problems: evidence from 3 independent genetically sensitive research designs. JAMA Psychiatry, 2013;70(9):956–963. Source for the link with conduct problems holding among children reared by genetically unrelated mothers. pmc.ncbi.nlm.nih.gov
Haan E, Westmoreland KE, Schellhas L, et al. Prenatal smoking, alcohol and caffeine exposure and offspring externalizing disorders: a systematic review and meta-analysis. Addiction, 2022;117(10):2602–2613. Source for findings on conduct disorder needing more genetically sensitive research. pmc.ncbi.nlm.nih.gov
Kendler KS, Aggen SH, Patrick CJ. Familial influences on conduct disorder reflect 2 genetic factors and 1 shared environmental factor. JAMA Psychiatry, 2013;70(1):78–86. Source for the 2,769 male twins in Virginia and the shared-environment factor linked to covert acts such as stealing. pmc.ncbi.nlm.nih.gov
Yang Y, Raine A. Prefrontal structural and functional brain imaging findings in antisocial, violent, and psychopathic individuals: a meta-analysis. Psychiatry Research: Neuroimaging, 2009;174(2):81–88. Source for the 43 studies, the effect size of -0.60, the three regions, the call for longitudinal imaging studies, the comparison of studies with and without comorbid disorders, and the 789 antisocial individuals, 83.9% of them male. pmc.ncbi.nlm.nih.gov
Tully J, Cross B, Gerrie B, Griem J, Blackwood N, Blair RJ, McCutcheon RA. A systematic review and meta-analysis of brain volume abnormalities in disruptive behaviour disorders, antisocial personality disorder and psychopathy. Nature Mental Health, 2023;1(3):163–173. Source for the 23 studies, the smaller total grey matter (-0.6) and amygdalas (-0.89) than in healthy controls, and the greater variability of total grey matter. doi.org research.regionh.dk
Mackey S, Allgaier N, Chaarani B, et al. Mega-analysis of gray matter volume in substance dependence: general and substance-specific regional effects. American Journal of Psychiatry, 2019;176(2):119–128. Source for the 3,240 people and the lower volume or thickness, with dependence on any of five substances, in regions including the medial orbitofrontal cortex. pmc.ncbi.nlm.nih.gov
Cite this article
TruthBased.org. "What Exactly Creates a Sociopath?" Updated October 2026. https://www.truthbased.org/what-exactly-creates-a-sociopath