Health & Medicine
Are Vaccines Safe and Effective?
The vaccines in routine use prevent the diseases they target, and their serious side effects are rare. Studies of about two million children found no link to autism.
Science & Media Accuracy
Is Climate Change Real and Human-Caused?
The IPCC puts 2011–2020 about 1.1 °C above 1850–1900 on four temperature records, and its best estimate of the human share at all of the warming.
Health & Medicine
Does Social Media Harm Teenagers’ Mental Health?
CDC survey data, meta-analyses, and where the evidence is thin.
Is Ultra-Processed Food Bad for You?
In the latest federal figures, ultra-processed food supplies more than half the calories Americans eat. This page sets out what the feeding trials, the cohort studies of death and disease, and the studies that split the ultra-processed group into kinds of food show, and where each falls short.
Jump to the verdict ↓
The short answer
Some of it probably is. In two controlled trials, people ate more, or lost less weight, on an ultra-processed diet than on an unprocessed or minimally processed one, over weeks rather than years. For disease and death there are only cohort studies, which mostly find small links to higher risk and cannot fully separate the food from the people who eat it. The clearest signals come from ultra-processed meat and sweetened drinks; the ultra-processed kinds of whole-grain bread, cereal and yogurt have mostly been linked to lower risk.
Ultra-processed is about how a food is made
The NOVA classification system sorts foods into four groups by the nature, extent and purpose of the industrial processing they have been through, not by the nutrients they contain. Carlos Monteiro’s team at the University of São Paulo devised the system.
| Group | Description | Examples |
|---|---|---|
| Group 1 | Unprocessed or minimally processed foods | Fresh fruit, vegetables, plain meat, eggs, milk, flour |
| Group 2 | Processed culinary ingredients | Cooking oils, butter, lard, salt, sugar |
| Group 3 | Processed foods (Group 1 foods with salt, oil, sugar or another Group 2 ingredient added) | Canned vegetables, salted nuts, cured meats, cheese |
| Group 4 | Ultra-processed foods (industrial formulations, made mostly from substances and additives rarely or never used in home cooking) | Packaged snacks, soft drinks, instant noodles, chicken nuggets, margarine, flavored yogurt, sweetened breakfast cereals |
The latest published round of the national nutrition survey run by the federal government, NHANES, ran from August 2021 to August 2023. Coded into the NOVA groups, its figures put ultra-processed food at 53% of calories for adults and 62% for children and teenagers. Both shares are a little lower than in 2017–2018 (National Center for Health Statistics, 2025).
What the feeding trials found
The first randomized controlled trial to test whether ultra-processed food makes people eat more was run by Kevin Hall and colleagues at the National Institutes of Health (Cell Metabolism, 2019). Offered ultra-processed and unprocessed meals matched for calories, carbohydrate, fat, protein, sugar, salt and fiber, people ate 508 more calories a day on the ultra-processed diet. They gained 0.9 kg in their two weeks on that diet. In their two weeks on the unprocessed diet, they lost 0.9 kg.
Because the diets were assigned at random, the trial can test cause and effect, which studies of what people choose to eat, such as cohort studies, cannot. The volunteers lived on a hospital ward, eating as much or as little as they wanted, so staff could weigh everything they ate. The trial was small (20 people) and short (two weeks on each diet), and a hospital ward is not a kitchen at home.
The trial was not built to find out why people ate more. Its authors offer three candidates: people ate faster on the ultra-processed diet, its solid food packed more calories into each gram, and it supplied slightly less protein.
The 2025 UPDATE trialA later trial, known as UPDATE, compared minimally processed and ultra-processed diets that both followed UK government healthy-eating advice (Dicken and colleagues, Nature Medicine, 2025). Hall was among its authors. Participants lost more weight on the minimally processed diet (−2.06% of body weight) than on the ultra-processed one (−1.05%). The difference was about one percentage point (P = 0.024). That difference is roughly 1 kg.
Its 55 volunteers in England were overweight or obese and usually ate a lot of ultra-processed food. UPDATE was a crossover trial: each person was meant to eat both diets for eight weeks, delivered to their homes, with four weeks of their usual food in between. Of the volunteers, 43 finished both diets. In all, 50 gave weight data for at least one.
At eight weeks on each diet, UPDATE is the longest of the five trials that had fed people both kinds of diet by June 2026 (Magkos and colleagues, Science, 2026). Unlike the Hall trial, it ran with people living at home, closer to everyday life but with no way to measure exactly what was eaten.
In January 2026 Nature Medicine published three letters about the trial:
- Eric Robinson and Ciarán Forde argued that the two diets differed in their nutrition as well as in processing, in ways that could explain the result on their own.
- David Ludwig, Walter Willett and Mary Putt argued that, read conservatively, a difference of about 1 kg would matter little for public health. In their view, that difference does not justify adding food processing to dietary advice.
- Zixuan Wang and Can Peng listed features of the design that weaken the case for blaming processing, among them the dropouts and the order effect.
The trial’s authors replied to all three in the same issue.
What the cohort studies find on death and disease
Death from any cause in one cohort and one review
Adjusted for other risk factors; HR and RR are hazard and risk ratios, so 1.2 means a rate a fifth higher
Schnabel et al. 2019 (France, NutriNet-Santé, n=44,551, aged 45 and over)HR 1.14 per 10-point rise in the ultra-processed share of food weight (1.04–1.27)
Liang et al. 2025 meta-analysis (18 cohorts, n=1,148,387)HR 1.15 highest vs. lowest intake (15 cohorts); HR 1.10 per 10-point rise in the ultra-processed share (10 cohorts)
Srour et al. (BMJ, 2019) followed 105,159 adults in the NutriNet-Santé cohort for a median of 5.2 years. Fiolet et al. (BMJ, 2018), working in the same cohort, reported on overall cancer.
| Outcome | Hazard ratio (95% confidence interval) | Study |
|---|---|---|
| Overall cardiovascular disease | 1.12 (1.05–1.20) | Srour et al. 2019 |
| Coronary heart disease | 1.13 (1.02–1.24) | Srour et al. 2019 |
| Cerebrovascular disease | 1.11 (1.01–1.21) | Srour et al. 2019 |
| Overall cardiovascular disease, share measured by energy | 1.06 (1.01–1.12) | Srour et al. 2019 |
| Overall cancer | 1.12 (1.06–1.18) | Fiolet et al. 2018 |
Measured by energy instead, the excess risk for overall cardiovascular disease was half the size. The hazard ratios are small, from 1.06 to 1.13, and most large cohorts point the same way. Liang et al., pooling 18 cohorts in 2025, noted three large recent ones that found no association.
Higher risk per 10-point rise in the ultra-processed share of the diet
How to read it: each bar shows how much higher the risk of its outcome was, in percent, per 10 percentage point rise in the ultra-processed share of the diet. A bar of 12 means a 12% higher risk, a ratio of 1.12, not 12 extra cases in every 100 people. Death from any cause, 10%, is the 2025 pool of 10 cohorts by Liang et al. Type 2 diabetes, 12%, is the figure Lane et al.’s 2024 umbrella review of meta-analyses reports from seven pooled cohorts. Cardiovascular disease, 12%, is Srour et al. 2019. The three bars share a unit but not a measurement. Srour’s share and the diabetes pool behind Lane’s figure are of food weight, while Liang’s pool counts shares of weight and of energy as the same thing. All three are associations in people’s reported diets, not proof that the food caused the disease.
| Outcome | Higher risk per 10-point rise | Ratio (95% confidence interval) | Source |
|---|---|---|---|
| Death from any cause | 10% | Hazard ratio 1.10 (1.04–1.16) | Liang et al. 2025, 10 cohorts pooled |
| Type 2 diabetes | 12% | Risk ratio 1.12 (1.11–1.13) | Lane et al. 2024, seven cohorts pooled |
| Cardiovascular disease | 12% | Hazard ratio 1.12 (1.05–1.20) | Srour et al. 2019 |
Every cohort study here shares one weakness, called confounding. The heaviest consumers of ultra-processed food differ from the rest in other ways, some of which raise the risk of death and disease on their own. In the French NutriNet-Santé cohort the heaviest consumers had lower incomes and less education, smoked more and exercised less.
Srour’s models took account of body mass, education, exercise, smoking, alcohol and calories, then of the nutritional quality of the diet, and the link with cardiovascular disease held. Schnabel’s mortality models also allowed for household income and for a score of diet quality. The link with death held too, though a model can adjust only for what was measured, and measured well.
How ultra-processed food might cause harm, and what has been tested
| Proposed cause | What it rests on | What the evidence shows |
|---|---|---|
| Eating faster, and so eating more | One inpatient trial of 20 adults (Hall 2019); a 2026 trial of 41 adults on two ultra-processed diets (Forde 2026) | In the Hall trial, people ate about 500 more calories a day on the ultra-processed diet and ate faster. Their ratings of the two diets for pleasantness and familiarity, and of hunger and fullness, showed no clear difference, which the authors take to mean the extra eating was not down to taste. They suggest softer food may have sped up eating and delayed the signals that end a meal, but the trial was not designed to find the cause. In a 2026 trial, 41 adults ate about 370 fewer calories a day on an ultra-processed diet built from foods whose texture slows eating than on one eaten faster, though over two weeks their weight did not differ (Forde 2026). |
| Food structure broken down in processing (matrix disruption) | Two reviews that disagree | The idea is that processing breaks down the structure of whole foods (the food matrix), so food is eaten and digested faster. A 2025 review in the Lancet, led by Carlos Monteiro, whose team devised NOVA, counts disrupted food matrices among the causes of overeating. A 2023 critical review found that direct comparisons of ultra-processed and other food on fiber, texture, how fast the stomach empties and how fast food moves through the gut did not show an effect special to ultra-processed food. |
| Energy density and very tasty (hyperpalatable) food | The Hall trial, and the 2025 Lancet review | Leaving drinks aside, the ultra-processed food in the Hall trial held about 85% more calories per gram, and the authors think this likely added to the overeating. The Lancet review counts both energy density and very tasty food among the causes of overeating; in the Hall trial, taste ratings showed no clear difference between the diets. |
| Additives such as emulsifiers and artificial sweeteners | Studies in mice; two small, short trials in people | Studies in mice suggest some emulsifiers and sweeteners disturb gut bacteria. Two small trials in people found changes too. Over 11 days, the emulsifier carboxymethylcellulose made gut bacteria less varied in a trial of 16 healthy adults, and in a larger trial of healthy adults, two weeks of saccharin or sucralose worsened blood-sugar responses. Neither measured disease. |
| Compounds formed at high heat (advanced glycation end-products, or AGEs) | Small diet trials | In small trials, cutting AGEs lowered markers of inflammation, and two pooled analyses found lower insulin resistance, though blood sugar itself did not change; a review limited to people with diabetes found no change in insulin resistance. AGEs come from food cooked at high temperatures as well as from processing, so they are not special to ultra-processed food. |
| Crowding out fruit, vegetables and legumes (displacement) | Surveys of what people eat | In national diet surveys, people who get more of their calories from ultra-processed food get less of them from fruit, vegetables and legumes. The surveys catch the pattern at one moment and do not show that ultra-processed food is what pushed those foods out. |
Not every ultra-processed food carries the same risk
NOVA’s ultra-processed group is broad. Large cohort studies that split the group into kinds of food find that the kinds behave differently, and not always in the same way from one disease to the next.
| Kind of food | What was found | Direction |
|---|---|---|
| Processed meats | HR 1.15 for type 2 diabetes (Li 2024, 31 cohorts pooled) and RR 1.16 for colorectal cancer (World Cancer Research Fund), each per 50 g a day, about one hot dog, for all processed meat | Higher risk |
| Sugar-sweetened beverages | RR 1.18 for type 2 diabetes per serving a day, 1.13 after adjusting for body weight (Imamura 2015, 17 cohorts pooled) | Higher risk |
| Packaged bread and breakfast cereals | Lower risk of type 2 diabetes for cereals and for whole-grain and dark breads, higher for refined breads (Chen 2023); for bread and cereals counted together, lower risk of cardiovascular disease (Mendoza 2024) and no link in a European cohort (Cordova 2023); ultra-processed breads and breakfast foods, counted together, linked to slightly higher death rates (Fang 2024) | Mixed; depends on the bread |
| Yogurt and dairy desserts | Lower risk of type 2 diabetes (Chen 2023), of cardiovascular disease (Mendoza 2024) and of colorectal cancer in women (Wang 2022); dairy desserts linked to slightly higher death rates (Fang 2024) | Mixed, mostly lower |
| Plant-based alternatives | No link with developing two or more of cancer, cardiovascular disease and type 2 diabetes (Cordova 2023), and lower risk of type 2 diabetes (Dicken 2024), in the same large European cohort | No link or lower, one cohort |
Two kinds stand out. Ultra-processed meat and other animal-based products, and sweetened drinks, were linked to higher risk in each of four studies. Chen 2023 studied type 2 diabetes, Fang 2024 deaths and Mendoza 2024 cardiovascular disease. Cordova 2023 studied developing at least two of cancer, cardiovascular disease and type 2 diabetes. All but Mendoza 2024 count diet drinks together with sugary ones. The other kinds were mixed.
None of this clears everything made from grain or plants. In a study of about 118,000 adults in the UK Biobank cohort, ultra-processed food made from plants, taken as one group, was linked to more cardiovascular disease. Packaged bread was the largest part of that group (Rauber 2024).
The processed-meat figure in the table covers cured meats such as bacon, which NOVA does not always count as ultra-processed. The Food and Agriculture Organization’s description of the system puts bacon in the processed group. But the 2022 colorectal cancer study (Wang 2022) counted bacon, hot dogs, salami and sausages as ultra-processed meat.
The strongest case on each side
The trials carry the most weight. In the Hall 2019 trial, meals offered with the same calories and nutrients did not stop people eating about 500 more calories a day on the ultra-processed diet. In the UPDATE trial, people following the same healthy-eating advice lost about half as much weight on ultra-processed food as on minimally processed food. These results are causal evidence that an ultra-processed diet leads people to eat more or lose less, even though neither trial could say which feature of the food does it.
Large cohort studies add associations that point mostly the same way, for death and for disease. Liang et al.’s 2025 pool for mortality alone has 18 cohorts and more than a million people. There are also plausible ways the harm could happen: energy density and eating rate, matrix disruption and displacement. On this evidence, the case for harm is substantial.
Displacement matters even if nothing in the food is harmful in itself. Srour and colleagues argued that eating fewer foods that are not ultra-processed may explain part, but not all, of the link with cardiovascular disease in the French NutriNet-Santé cohort. Their reason is that several kinds of ultra-processed food were linked with cardiovascular disease where the same kinds of food, when not ultra-processed, were not.
The strongest case that the harm is overstatedThe observational evidence cannot establish causation due to confounding. In NutriNet-Santé the heaviest consumers were poorer and less educated, smoked more and exercised less, each carrying risk of its own. Monge and Lajous wrote the BMJ’s 2018 editorial on Fiolet’s cancer study. They argued that exercise and other risk factors are hard to measure, so confounding could still explain an association this weak.
The NOVA classification lumps foods with very different nutritional profiles and health effects into the same group. Yogurt and hot dogs are not comparable health risks. Reporting on type 2 diabetes in a large European cohort in 2024, Dicken and colleagues found some kinds of ultra-processed food linked with more diabetes and others with less. That finding, they wrote, questions using one overall ultra-processed measure in advice on diabetes and supports aiming at specific products instead.
The trials are few, small and short. Five trials had fed people both kinds of diet by June 2026. The longest, UPDATE, ran eight weeks on each diet with 55 volunteers. Its critics argue that its two diets differed in more than processing.
Scaling results like these up to disease over a lifetime requires assumptions the data cannot directly support. Lane and colleagues, who make the case for harm, say that only short trials of outcomes such as weight are feasible. Assigning people for years to a diet suspected of harm, to see who develops cardiovascular disease or cancer, would in their view be unethical.
The verdict: what the evidence shows
Some of it probably is. The firmest evidence is also the narrowest. In two controlled trials, people offered an ultra-processed diet ate more, or lost less weight, than on an unprocessed or minimally processed one. On a hospital ward they ate about 500 more calories a day (Hall 2019). At home they lost about 1 kg less weight over eight weeks (the British UPDATE trial, 2025).
Both trials ran for weeks, with 20 and 55 people, and neither could say which feature of the food was responsible. Critics of UPDATE argue that its two diets differed in more than processing.
For death and disease there are only cohort studies. Pooled, they find death rates about 15% higher among the heaviest consumers of ultra-processed food than among the lightest (Liang 2025). They also link heavy consumption with more type 2 diabetes and cardiovascular disease. Those are relative figures. In the French cohort behind the cardiovascular numbers, cardiovascular disease struck about 277 of every 100,000 of the heaviest consumers each year, against 242 of the lightest (Srour 2019).
The heaviest consumers in the French cohort were also poorer, smoked more and exercised less. Adjusting for that has not made the links disappear, but a model can only adjust for what it measures.
And the ultra-processed group is too broad to judge as one thing. In all four large studies that split it into kinds, ultra-processed meat and sweetened drinks were linked to higher risk, and whole-grain bread, cereal and yogurt mostly to lower. The evidence against those two kinds is firmer than the evidence against ultra-processed food as a whole.
Four common claims, against the evidence
Claim“Ultra-processed food is poison.”
OverstatedCohort studies link ultra-processed food with worse health on average, but the kinds of food inside the group differ. The ultra-processed kinds of whole-grain bread and yogurt went with lower risk of type 2 diabetes in large US cohorts, and yogurt with lower risk of cardiovascular disease. Plant-based alternatives showed no link, or a lower risk of type 2 diabetes, in a European cohort. Refined bread and dairy desserts went the other way in some studies.
Claim“Processed food is fine; it’s just calories.”
Not fully supportedThe Hall 2019 trial offered ultra-processed and unprocessed meals matched for calories, sugar, fat, fiber and the main nutrients. People ate 508 more calories a day on the ultra-processed diet. The trial was not built to show which feature of the food caused it; its authors point to faster eating and solid food that packed more calories into each gram.
Claim“Food additives are the main problem.”
Not shownAdditives are one of six proposed causes. Emulsifiers and sweeteners changed gut bacteria in mice and in two small, short trials in people, but no trial has run long enough to measure disease. The Hall trial points more to how fast people ate and how many calories the solid food packed into each gram.
Claim“Processed meat is the worst of it.”
Largely supportedUltra-processed meat, with sweetened drinks, was linked to higher risk in all four large studies that split ultra-processed food into kinds. Per 50 g a day, processed meat as a whole goes with a 15% higher rate of type 2 diabetes (Li 2024). The same amount goes with a 16% higher risk of colorectal cancer (World Cancer Research Fund). These are associations, and cured meats such as bacon are not always counted as ultra-processed.
Download the conclusion
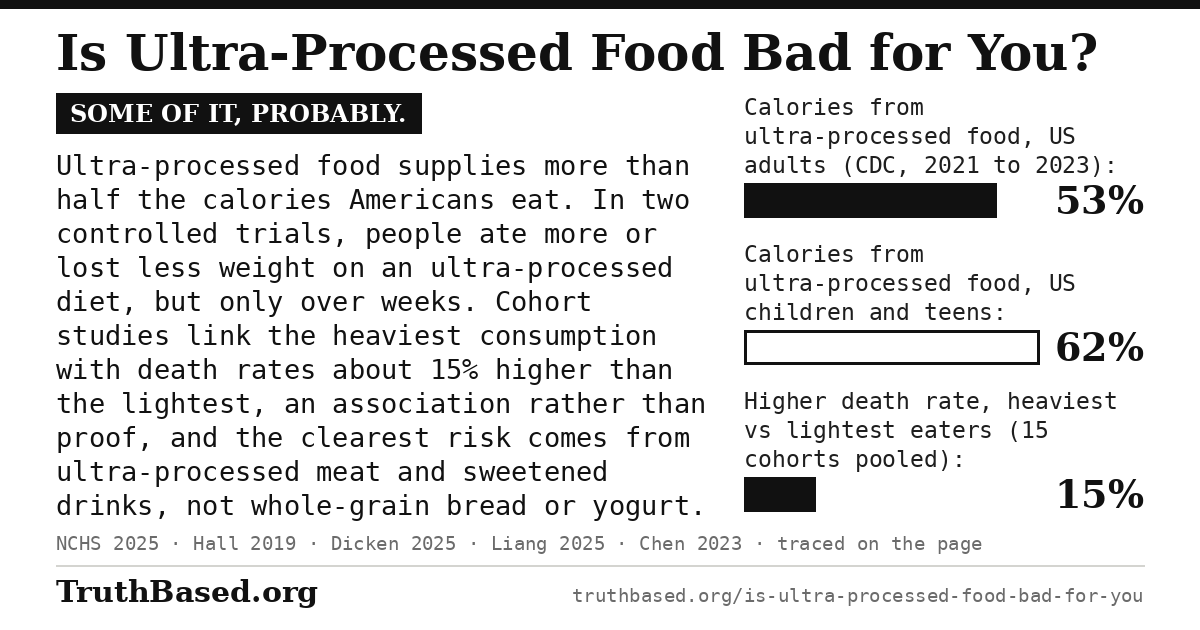
The verdict above as one image, with the three numbers that frame it. Two are the shares of Americans’ calories that come from ultra-processed food, for adults and for children and teenagers. The card also shows how much higher death rates run among the heaviest consumers than the lightest. It is 1,200 by 630 pixels, the size social networks use for link previews, and anyone may download it and post it.
What would change this conclusion
This article concludes that: (1) in two controlled trials an ultra-processed diet led people to eat more (about 500 calories a day, Hall 2019) or lose less weight (about 1 kg over eight weeks, UPDATE), for reasons the trials did not isolate; (2) pooled cohort studies link the highest ultra-processed intakes with death rates about 15% higher than the lowest (Liang 2025, 15 cohorts), an association and not a proven cause; (3) ultra-processed meat and sweetened drinks carry the most consistent risk signals; (4) the ultra-processed kinds of whole-grain bread, cereal and yogurt are mostly linked to lower risk in the studies that separate them, and plant-based alternatives showed no link, or a lower risk of type 2 diabetes, in a large European cohort.
These conclusions would be falsified by:
• Larger, longer trials (more than 200 people, more than six months) finding no difference in how much people eat, or in their weight, on matched ultra-processed and unprocessed diets
• Mendelian randomization studies, which use inherited genetic differences as a natural experiment, finding no causal link between ultra-processed food and health outcomes
• Large cohort studies that measure income, exercise and the other differences between heavy and light consumers more closely, finding that the higher risks shrink to nothing
• Evidence that whole-grain bread or yogurt harms health as much as processed meat
You May Also Like
TruthBased.org is reader-supported. You can contribute by card or PayPal, or with cryptocurrency, on the support page.
Sources
Monteiro CA, Cannon G, Lawrence M, Costa Louzada ML, Pereira Machado P. Ultra-processed foods, diet quality, and health using the NOVA classification system. Rome: Food and Agriculture Organization of the United Nations, 2019. Source for the four NOVA groups and their examples, and for NOVA’s origin with Carlos Monteiro’s team at the University of São Paulo. fao.org
Williams AM, Couch CA, Emmerich SD, Ogburn DF. Ultra-processed Food Consumption in Youth and Adults: United States, August 2021–August 2023. NCHS Data Brief No. 536. National Center for Health Statistics, August 2025. Source for the shares of calories from ultra-processed food in 2021–2023, 53% for adults and 62% for ages 1 to 18, and for their fall since 2017–2018. cdc.gov
Hall KD, et al. Ultra-Processed Diets Cause Excess Calorie Intake and Weight Gain: An Inpatient Randomized Controlled Trial of Ad Libitum Food Intake. Cell Metabolism, 2019;30(1):67–77.e3. Source for the trial of 20 adults on the NIH Clinical Center’s metabolic ward, two weeks on each diet in random order: 508 ± 106 more calories a day on the ultra-processed diet (P = 0.0001); weight changes of +0.9 kg and −0.9 kg; the matching of the meals offered, the 85% higher energy density of the solid food and the slightly lower protein; the eating rate and the ratings of pleasantness, familiarity, hunger and fullness; and the authors’ view that softer food may have sped up eating and delayed the signals that end a meal. cell.com pmc.ncbi.nlm.nih.gov
Magkos F, Forde CG, Robinson E. Ultraprocessed foods and obesity: interpreting the evidence. Science, 2026;392(6802):1020–1022. Source for the five randomized trials that had fed people both ultra-processed and less processed diets by June 2026, and UPDATE’s eight weeks as the longest. science.org
Dicken SJ, et al. Ultraprocessed or minimally processed diets following healthy dietary guidelines on weight and cardiometabolic health: a randomized, crossover trial. Nature Medicine, 4 August 2025, 31:3297–3308. Source for the UPDATE trial, whose authors include Kevin Hall: 55 adults randomised, 50 in the intention-to-treat analysis and 43 completing both diets, eight weeks on each diet with the food delivered to their homes and a four-week washout between; weight change of −2.06% on the minimally processed diet against −1.05% on the ultra-processed one (P = 0.024). nature.com
Robinson E, Forde CG. Concerns around evidence that food processing should be included in dietary guidance. Nature Medicine, 2026;32:465–467 (Matters Arising). Argues that the two UPDATE diets differed in nutrition in ways that could explain the result without processing. nature.com
Ludwig DS, Willett WC, Putt ME. Concerns over conclusions in an ultra-processed food trial. Nature Medicine, 2026;32:463–464 (Matters Arising). Argues that a difference of about 1 kg would matter little for public health and does not justify adding food processing to dietary advice. nature.com
Wang Z, Peng C. Concerns about attributing weight change to processing in a crossover feeding trial. Nature Medicine, 2026;32:468–469 (Matters Arising). Lists features of the UPDATE design that weaken the case for blaming processing, among them the dropouts and the order effect. nature.com
Dicken SJ, Brown A, Batterham RL. Reply to Ludwig, D. S. et al.; Robinson, E. & Forde, C. G.; Wang, Z. & Peng, C. Nature Medicine, 2026;32:470–471. The UPDATE authors’ reply to all three letters, in the same issue. nature.com
Schnabel L, Kesse-Guyot E, Allès B, et al. Association Between Ultraprocessed Food Consumption and Risk of Mortality Among Middle-aged Adults in France. JAMA Internal Medicine, 2019;179(4):490–498. Source for the French mortality row: 44,551 NutriNet-Santé participants aged 45 and over, 602 deaths over a median 7.1 years, hazard ratio 1.14 (1.04–1.27) per 10-point rise in the share of food weight from ultra-processed foods; and for its adjustment for household income and diet quality. pubmed.ncbi.nlm.nih.gov
Lane MM, et al. Ultra-processed food exposure and adverse health outcomes: umbrella review of epidemiological meta-analyses. BMJ, 2024;384:e077310. Source for the pooled figure for type 2 diabetes (risk ratio 1.12, 1.11–1.13, per 10-point rise in the share of food weight, seven cohorts), and for the authors’ view that long trials of disease could not be run, for ethical reasons. bmj.com
Liang S, Zhou Y, Zhang Q, Yu S, Wu S. Ultra-processed foods and risk of all-cause mortality: an updated systematic review and dose-response meta-analysis of prospective cohort studies. Systematic Reviews, 2025;14:53. Source for the mortality row and the first bar of the second chart: 18 cohorts, 1,148,387 participants and 173,107 deaths; hazard ratio 1.15 (1.09–1.22) for the highest against the lowest intake (15 cohorts) and 1.10 (1.04–1.16) per 10-point rise in the share of the diet (10 cohorts), a pool that counts shares of weight and of energy as the same; and the three large recent cohorts that found no association. systematicreviewsjournal.biomedcentral.com
Li C, Bishop TRP, Imamura F, et al. Meat consumption and incident type 2 diabetes: an individual-participant federated meta-analysis of 1.97 million adults with 100 000 incident cases from 31 cohorts in 20 countries. The Lancet Diabetes & Endocrinology, 2024;12(9):619–630. Source for the processed-meat figure: 31 cohorts, hazard ratio 1.15 (1.11–1.20) per 50 g of processed meat a day, adjusted for body mass index among other factors. thelancet.com
Imamura F, O’Connor L, Ye Z, et al. Consumption of sugar sweetened beverages, artificially sweetened beverages, and fruit juice and incidence of type 2 diabetes: systematic review, meta-analysis, and estimation of population attributable fraction. BMJ, 2015;351:h3576. Source for the sugar-sweetened beverage figure: 17 cohorts, 18% higher incidence per serving a day (9–28%) before adjustment for body fat and 13% after. doi.org
Srour B, et al. Ultra-processed food intake and risk of cardiovascular disease: prospective cohort study (NutriNet-Santé). BMJ, 2019;365:l1451. Source for the cardiovascular figures: 105,159 adults followed for a median 5.2 years; hazard ratios per 10-point rise in the share of the diet by weight of 1.12 (1.05–1.20) for cardiovascular disease, 1.13 (1.02–1.24) for coronary heart disease and 1.11 (1.01–1.21) for cerebrovascular disease, and 1.06 (1.01–1.12) when the share is measured by energy; incidence of 277 per 100,000 person-years in the top quarter of consumption against 242 in the bottom; the adjustment for diet quality; and the authors’ view that eating fewer foods that are not ultra-processed may explain part of the link but not all. pubmed.ncbi.nlm.nih.gov
Fiolet T, et al. Consumption of ultra-processed foods and cancer risk: results from NutriNet-Santé prospective cohort. BMJ, 2018;360:k322. Source for the hazard ratio of 1.12 (1.06–1.18) for overall cancer per 10-point rise in the share of the diet by weight, among 104,980 adults. bmj.com
Forde CG, Heuven LAJ, van Bruinessen M, et al. Eating rate has sustained effects on energy intake from ultraprocessed diets: a 2-week ad libitum dietary randomized controlled crossover trial. The American Journal of Clinical Nutrition, 2026;123(4):101122. Source for the trial of 41 adults on two ultra-processed diets, one built from foods whose texture slows eating: about 370 fewer calories a day on the slower diet (369, 221–517), with no difference in weight. pmc.ncbi.nlm.nih.gov
Monteiro CA, Louzada MLC, Steele-Martinez E, et al. Ultra-processed foods and human health: the main thesis and the evidence. The Lancet, 2025;406(10520):2667–2684. Source for the review that counts disrupted food matrices, energy density and very tasty food among the causes of overeating. thelancet.com
Valicente VM, Peng CH, Pacheco KN, et al. Ultraprocessed foods and obesity risk: a critical review of reported mechanisms. Advances in Nutrition, 2023;14(4):718–738. Source for the finding that direct comparisons of fiber, texture, stomach emptying and gut transit did not show an effect special to ultra-processed food. pmc.ncbi.nlm.nih.gov
Chassaing B, Compher C, Bonhomme B, et al. Randomized controlled-feeding study of dietary emulsifier carboxymethylcellulose reveals detrimental impacts on the gut microbiota and metabolome. Gastroenterology, 2022;162(3):743–756. Source for the 11-day trial of 16 healthy adults in which the emulsifier made gut bacteria less varied. pure.psu.edu
Suez J, Cohen Y, Valdes-Mas R, et al. Personalized microbiome-driven effects of non-nutritive sweeteners on human glucose tolerance. Cell, 2022;185(18):3307–3328. Source for the trial in healthy adults in which two weeks of saccharin or sucralose worsened blood-sugar responses. bugsigdb.org
Clarke RE, Dordevic AL, Tan SM, Ryan L, Coughlan MT. Dietary advanced glycation end products and risk factors for chronic disease: a systematic review of randomised controlled trials. Nutrients, 2016;8(3):125. Source for the small trials in which cutting AGEs lowered markers of inflammation. ncbi.nlm.nih.gov
Baye E, Kiriakova V, Uribarri J, Moran LJ, de Courten B. Consumption of diets with low advanced glycation end products improves cardiometabolic parameters: meta-analysis of randomised controlled trials. Scientific Reports, 2017;7:2266. With the next entry, one of the two pooled analyses that found lower insulin resistance on diets low in AGEs, with no change in blood sugar itself. ncbi.nlm.nih.gov
Sohouli MH, Fatahi S, Sharifi-Zahabi E, et al. The impact of low advanced glycation end products diet on metabolic risk factors. Advances in Nutrition, 2021;12(3):766–776. The second of the two pooled analyses. pmc.ncbi.nlm.nih.gov
Detopoulou P, Voulgaridou G, Seva V, et al. Dietary restriction of advanced glycation end-products (AGEs) in patients with diabetes: a systematic review of randomized controlled trials. International Journal of Molecular Sciences, 2024;25(21):11407. Source for the finding of no change in insulin resistance in people with diabetes. ncbi.nlm.nih.gov
Martini D, et al. Ultra-processed foods and nutritional dietary profile: a meta-analysis of nationally representative samples. Nutrients, 2021;13(10):3390. With the next entry, source for the finding that people who get more of their calories from ultra-processed food get less of them from fruit, vegetables and legumes. pubmed.ncbi.nlm.nih.gov
Martínez Steele E, Popkin BM, Swinburn B, Monteiro CA. The share of ultra-processed foods and the overall nutritional quality of diets in the US. Population Health Metrics, 2017;15:6. The same pattern in US national survey data. pophealthmetrics.biomedcentral.com
Chen Z, Khandpur N, Desjardins C, et al. Ultra-Processed Food Consumption and Risk of Type 2 Diabetes: Three Large Prospective U.S. Cohort Studies. Diabetes Care, 2023;46(7):1335–1344. Source for the type 2 diabetes findings by kind of food, higher risk for refined breads, sweetened drinks and animal-based products and lower for cereals, dark and whole-grain breads, and yogurt and dairy-based desserts; and for the pooled diabetes figure behind Lane’s 1.12. pubmed.ncbi.nlm.nih.gov
Fang Z, Rossato SL, Hang D, et al. Association of ultra-processed food consumption with all cause and cause specific mortality: population based cohort study. BMJ, 2024;385:e078476. Source for death rates by kind of food: meat-based ready-to-eat products and sweetened drinks among the kinds linked to higher death rates, and slightly higher rates for dairy-based desserts and for breads and breakfast foods counted together. pubmed.ncbi.nlm.nih.gov
Mendoza K, Smith-Warner SA, Rossato SL, et al. Ultra-processed foods and cardiovascular disease: analysis of three large US prospective cohorts and a systematic review and meta-analysis of prospective cohort studies. The Lancet Regional Health – Americas, 2024;37:100859. Source for cardiovascular disease by kind of food, lower risk for bread and cold cereals and for yogurt and dairy desserts, and higher for processed meats and sweetened drinks. thelancet.com
Cordova R, Viallon V, Fontvieille E, et al. Consumption of ultra-processed foods and risk of multimorbidity of cancer and cardiometabolic diseases: a multinational cohort study. The Lancet Regional Health – Europe, 2023;35:100771. Source for the European findings on developing at least two of cancer, cardiovascular disease and type 2 diabetes by kind of food: higher risk for animal-based products and sweetened drinks, no link for plant-based alternatives or for breads and cereals. thelancet.com
Wang L, Du M, Wang K, et al. Association of ultra-processed food consumption with colorectal cancer risk among men and women: results from three prospective US cohort studies. BMJ, 2022;378:e068921. Source for colorectal cancer by kind of food, lower risk in women for yogurt and dairy desserts; its ultra-processed meat group included bacon, hot dogs, salami and sausages. ncbi.nlm.nih.gov
Rauber F, Louzada MLC, Chang K, et al. Implications of food ultra-processing on cardiovascular risk considering plant origin foods: an analysis of the UK Biobank cohort. The Lancet Regional Health – Europe, 2024;43:100948. Source for the finding that ultra-processed food made from plants, taken as one group, was linked to more cardiovascular disease among about 118,000 adults, and that packaged bread was the largest part of that group. pmc.ncbi.nlm.nih.gov
World Cancer Research Fund / American Institute for Cancer Research. Continuous Update Project Expert Report 2018: Diet, nutrition, physical activity and colorectal cancer (first issued 2017). Source for the risk ratio of 1.16 for colorectal cancer per 50 g of processed meat a day. wcrf.org
U.S. Department of Agriculture, Agricultural Research Service. FoodData Central: Frankfurter, beef, unheated (SR Legacy, FDC ID 173862), 2019. Source for the weight of one hot dog, 49 g, behind “about one hot dog” for 50 g of processed meat. fdc.nal.usda.gov
Food and Agriculture Organization of the United Nations. The State of Food Security and Nutrition in the World 2023, Annex 5. Source for the Food and Agriculture Organization’s description of NOVA that puts un-reconstituted processed meat such as ham and bacon in the processed group. fao.org
Dicken SJ, Dahm CC, Ibsen DB, et al. Food consumption by degree of food processing and risk of type 2 diabetes mellitus: a prospective cohort analysis of the European Prospective Investigation into Cancer and Nutrition (EPIC). The Lancet Regional Health – Europe, 2024;46:101043. Source for the lower type 2 diabetes risk with plant-based alternatives, and for the policy argument in the case that the harm is overstated: some ultra-processed groups went with more type 2 diabetes and others with less, and the authors wrote that this questions one overall ultra-processed measure in advice on diabetes. The same first author as the UPDATE trial; a different study. pmc.ncbi.nlm.nih.gov
Monge A, Lajous M. Ultra-processed foods and cancer: the possibility of a link deserves further careful exploration. BMJ, 2018;360:k599 (editorial). Source for the argument that leftover confounding could explain an association as weak as Fiolet’s, since exercise and other risk factors are hard to measure. doi.org
Cite this article
TruthBased.org. “Is Ultra-Processed Food Bad for You?” Updated September 2026. https://www.truthbased.org/is-ultra-processed-food-bad-for-you